

by Jason Wasserman MD PhD FRCPC
August 12, 2026
Flat epithelial atypia (FEA) is a non-cancerous change in the small glands of the breast called terminal duct lobular units. In flat epithelial atypia, the normal cells lining these glands are replaced by one or more layers of mildly abnormal cells. The cells are usually cuboidal or column-shaped and can look similar to the cells found in certain early, low-grade breast cancers, but flat epithelial atypia itself is not cancer.
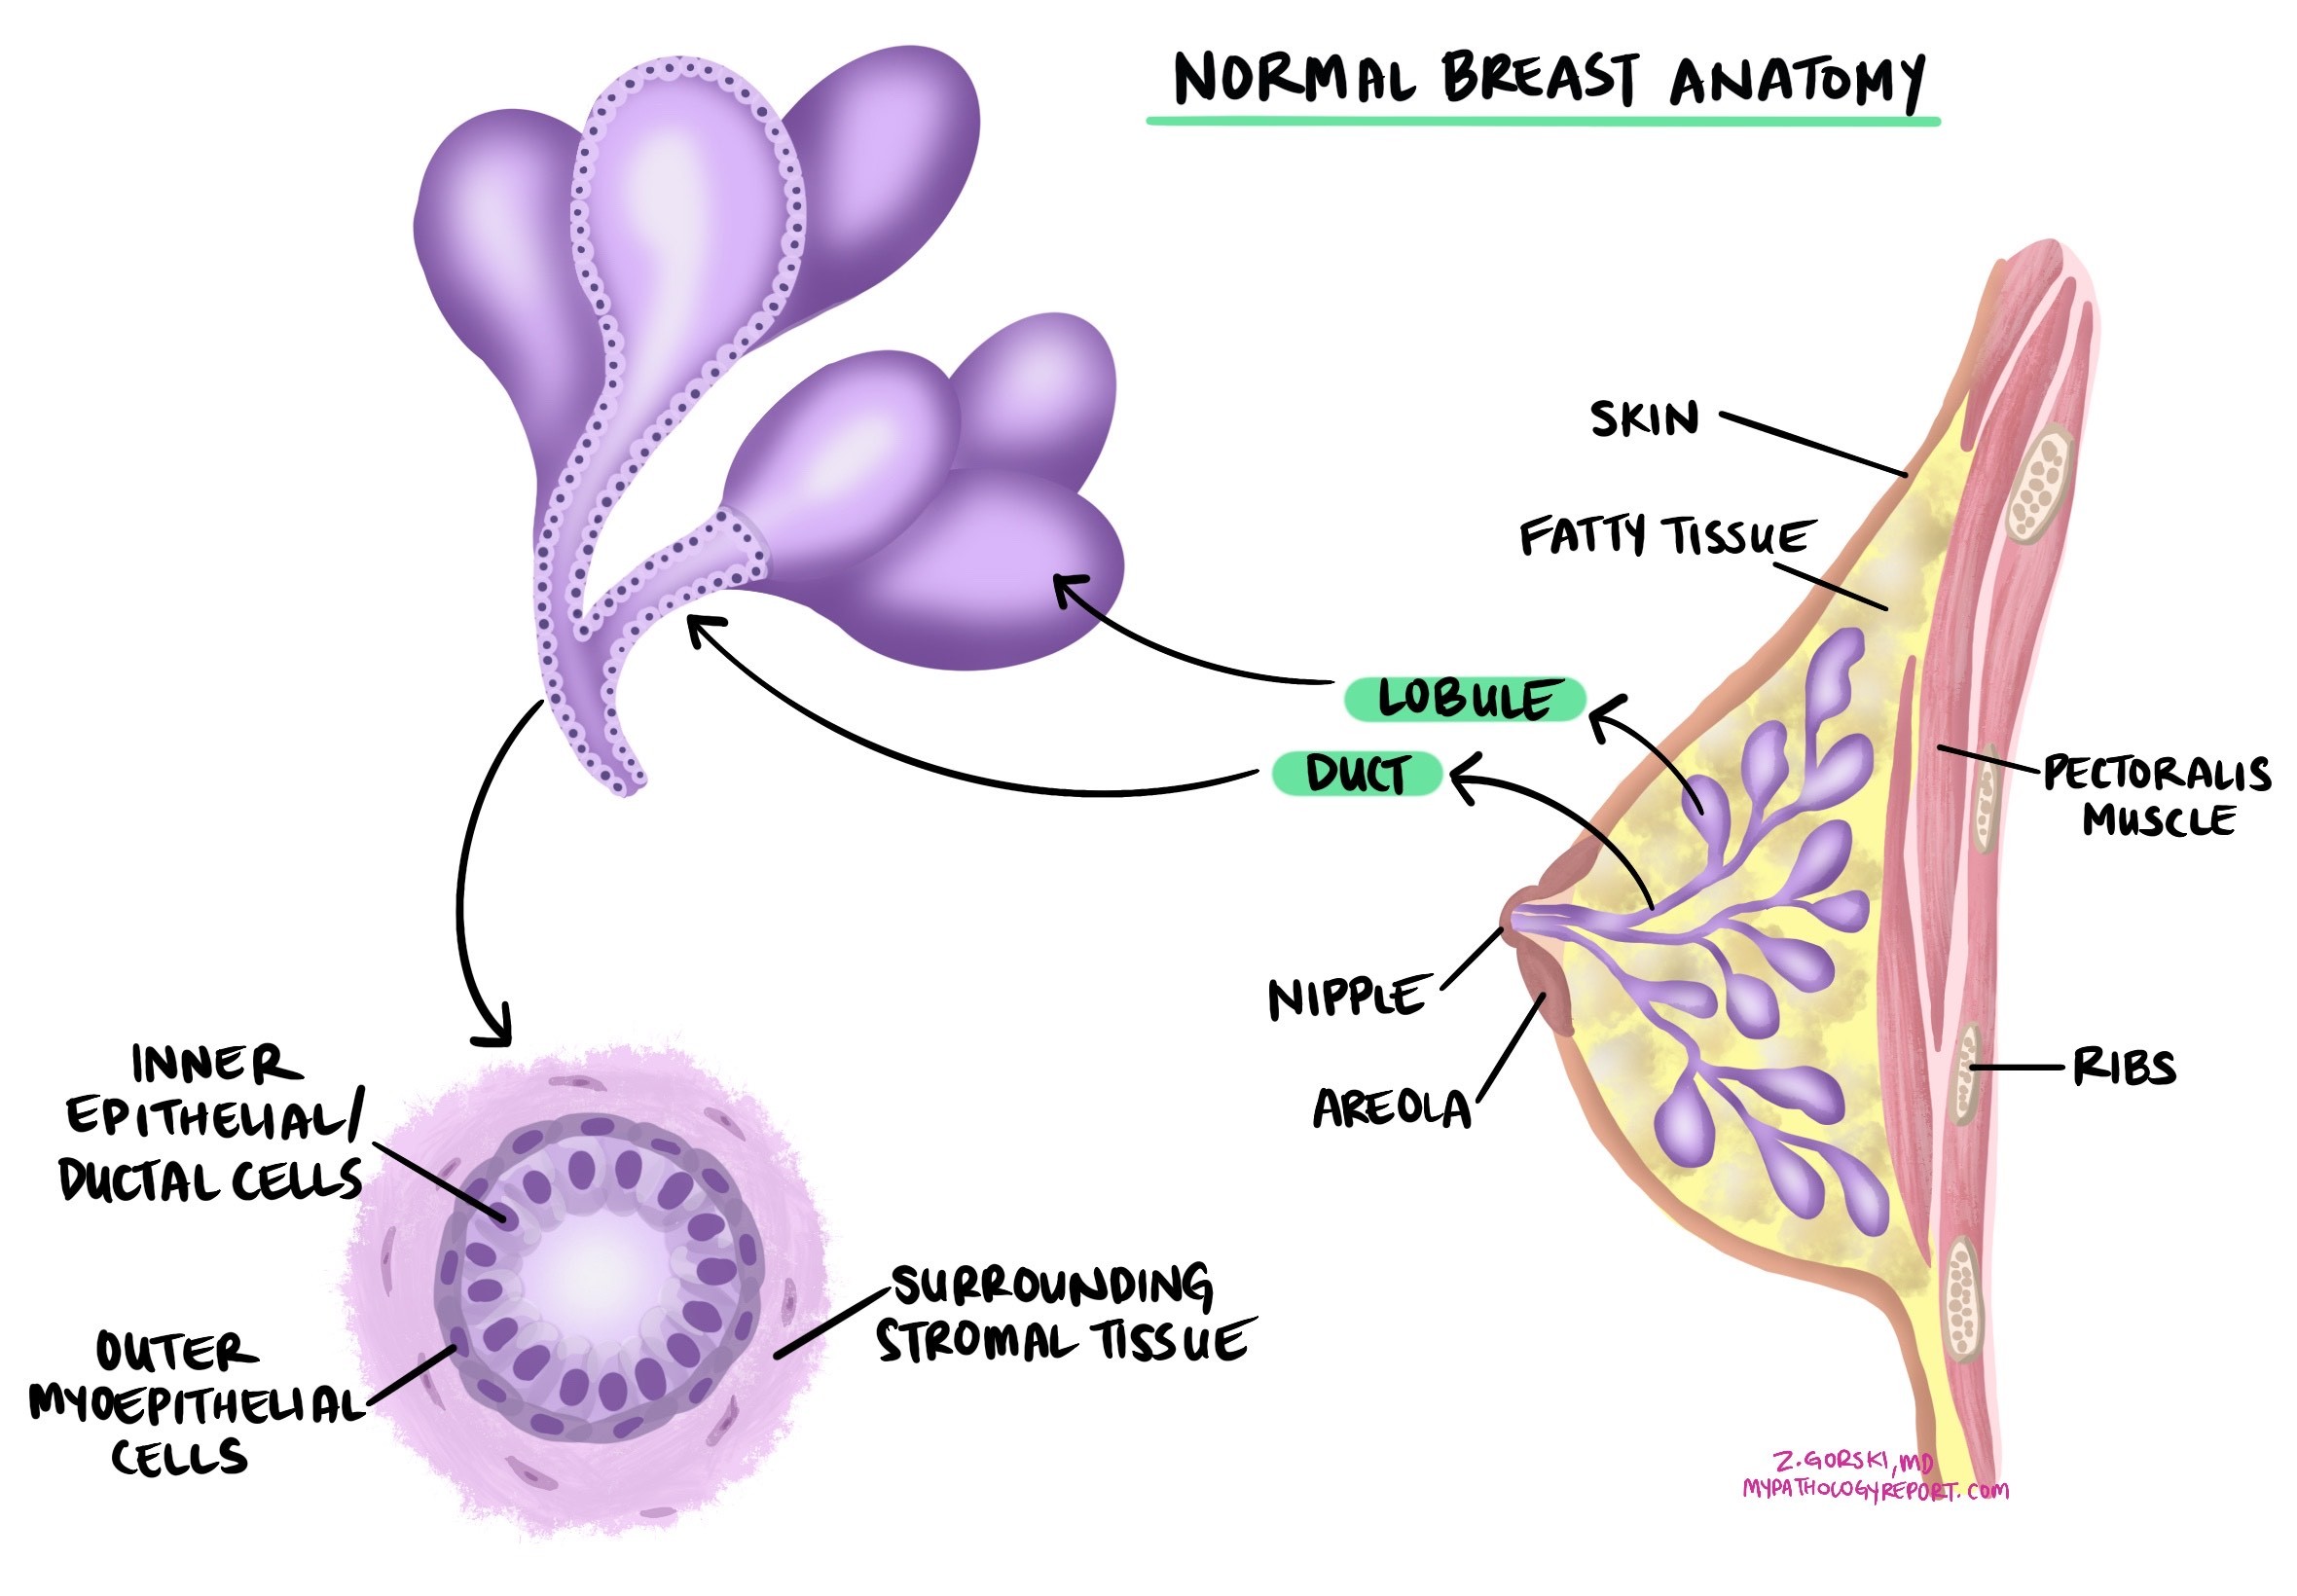
Flat epithelial atypia is part of a group of breast changes called columnar cell lesions, which also includes columnar cell change and columnar cell hyperplasia. Among these, flat epithelial atypia is the only one with atypia, a word pathologists use to describe cells that look different from normal under the microscope. Compared with the other breast changes that carry the word “atypical,” flat epithelial atypia is associated with the lowest increase in future breast cancer risk. This article will help you understand the findings in your pathology report, what each term means, and why it matters for your care.
Is flat epithelial atypia a type of cancer?
No. Flat epithelial atypia is not breast cancer, and the abnormal cells cannot spread to other parts of the body. It can sometimes be found alongside other, higher-risk changes, and in rare cases it may be a very early step toward certain low-grade breast cancers. Most people with flat epithelial atypia never develop breast cancer as a result of this finding.
What causes flat epithelial atypia?
The exact cause of flat epithelial atypia is not fully understood. Research has shown that it shares many biological and molecular features with other low-grade breast lesions, such as atypical ductal hyperplasia (ADH), low-grade ductal carcinoma in situ (DCIS), and some low-grade invasive cancers such as tubular carcinoma. These similarities include specific genetic changes, such as the loss of part of chromosome 16 (called 16q loss). Because of these shared features, flat epithelial atypia is considered an early step in what pathologists call the low-grade breast neoplasia pathway, a sequence of changes that can, in some cases, lead to certain low-grade breast cancers. These changes occur within the breast cells themselves and are not inherited.
What are the symptoms of flat epithelial atypia?
Flat epithelial atypia does not cause any symptoms. It is a microscopic change that cannot be felt during a breast examination. Most cases are found during a screening mammogram, often because of microcalcifications, which are tiny deposits of calcium that show up as small white spots on the mammogram. Less often, flat epithelial atypia is found by chance when a biopsy is done for another reason.
How is the diagnosis made?
The diagnosis of flat epithelial atypia is made after a sample of breast tissue is examined under the microscope by a pathologist. The tissue is most often collected with a core needle biopsy, usually after a mammogram shows microcalcifications. Under the microscope, the glands in the affected lobules are enlarged and lined by one to several layers of uniform, mildly atypical cells. These cells often have small, round nuclei with evenly distributed chromatin (the DNA inside the nucleus) and small, hard-to-see nucleoli.
The cells may have small projections called apical snouts, and the glands often contain secretions or microcalcifications. The growth pattern is flat, meaning there are no complex structures such as bridges, arches, or finger-like projections. This flat pattern is what separates flat epithelial atypia from more advanced changes such as low-grade ductal carcinoma in situ, in which the cells form these more complex structures.
What is the risk of developing breast cancer?
Flat epithelial atypia is best thought of as a marker of a small increase in the future risk of breast cancer. This increase is much lower than the risk associated with atypical ductal hyperplasia (ADH) or atypical lobular hyperplasia (ALH), and for most people the overall outlook is excellent. The level of risk also depends on whether other, higher-risk changes are present in the same biopsy. Most people with flat epithelial atypia never develop breast cancer as a result of this finding.
What happens after this diagnosis?
Because flat epithelial atypia is a low-risk change rather than a cancer, the goal after diagnosis is to make sure no more advanced change is present nearby and to plan appropriate follow-up. An important first step is radiology-pathology correlation, which means comparing the biopsy result with the mammogram to make sure they fit together. The pathology findings guide which options the team discusses, rather than dictating a single path.
- Observation — When flat epithelial atypia is the only finding and the biopsy result matches the imaging, close follow-up is often recommended rather than surgery, because the chance of finding a more advanced change is low.
- Surgical excision — Removing more tissue may be recommended when the biopsy result does not match the imaging, when the area seen on the mammogram was not fully removed, or when another higher-risk change is present in the same sample.
- Follow-up imaging — Your healthcare team will use your overall risk factors to decide on the right schedule for future breast screening.
Questions to ask your doctor
- Was flat epithelial atypia the only finding in my biopsy, or were other changes also present?
- Did the biopsy remove all of the area that showed on my mammogram?
- Did my biopsy result match my imaging findings?
- Do I need any further surgery, or is close follow-up enough in my case?
- How does this finding change my overall breast cancer risk?
- How often should I have mammograms or other imaging after this finding?
- Were any higher-risk changes, such as atypical ductal hyperplasia, found as well?
- What signs or symptoms should prompt me to contact you between visits?
Related articles on MyPathologyReport.com
- Columnar Cell Change of the Breast: Understanding Your Pathology Report
- Columnar Cell Hyperplasia of the Breast: Understanding Your Pathology Report
- Atypical Ductal Hyperplasia (ADH): Understanding Your Pathology Report
- Atypical Lobular Hyperplasia of the Breast: Understanding Your Pathology Report
- Ductal Carcinoma In Situ (DCIS) of the Breast: Understanding Your Pathology Report
- Understanding Your Breast Biopsy Pathology Report
We are proud to partner with:


🔍 Search MyPathologyReport
Type what you see on your report — for example a diagnosis or test name