

Section Editor: Kianoosh Keyhanian MD FRCPC
September 1, 2026
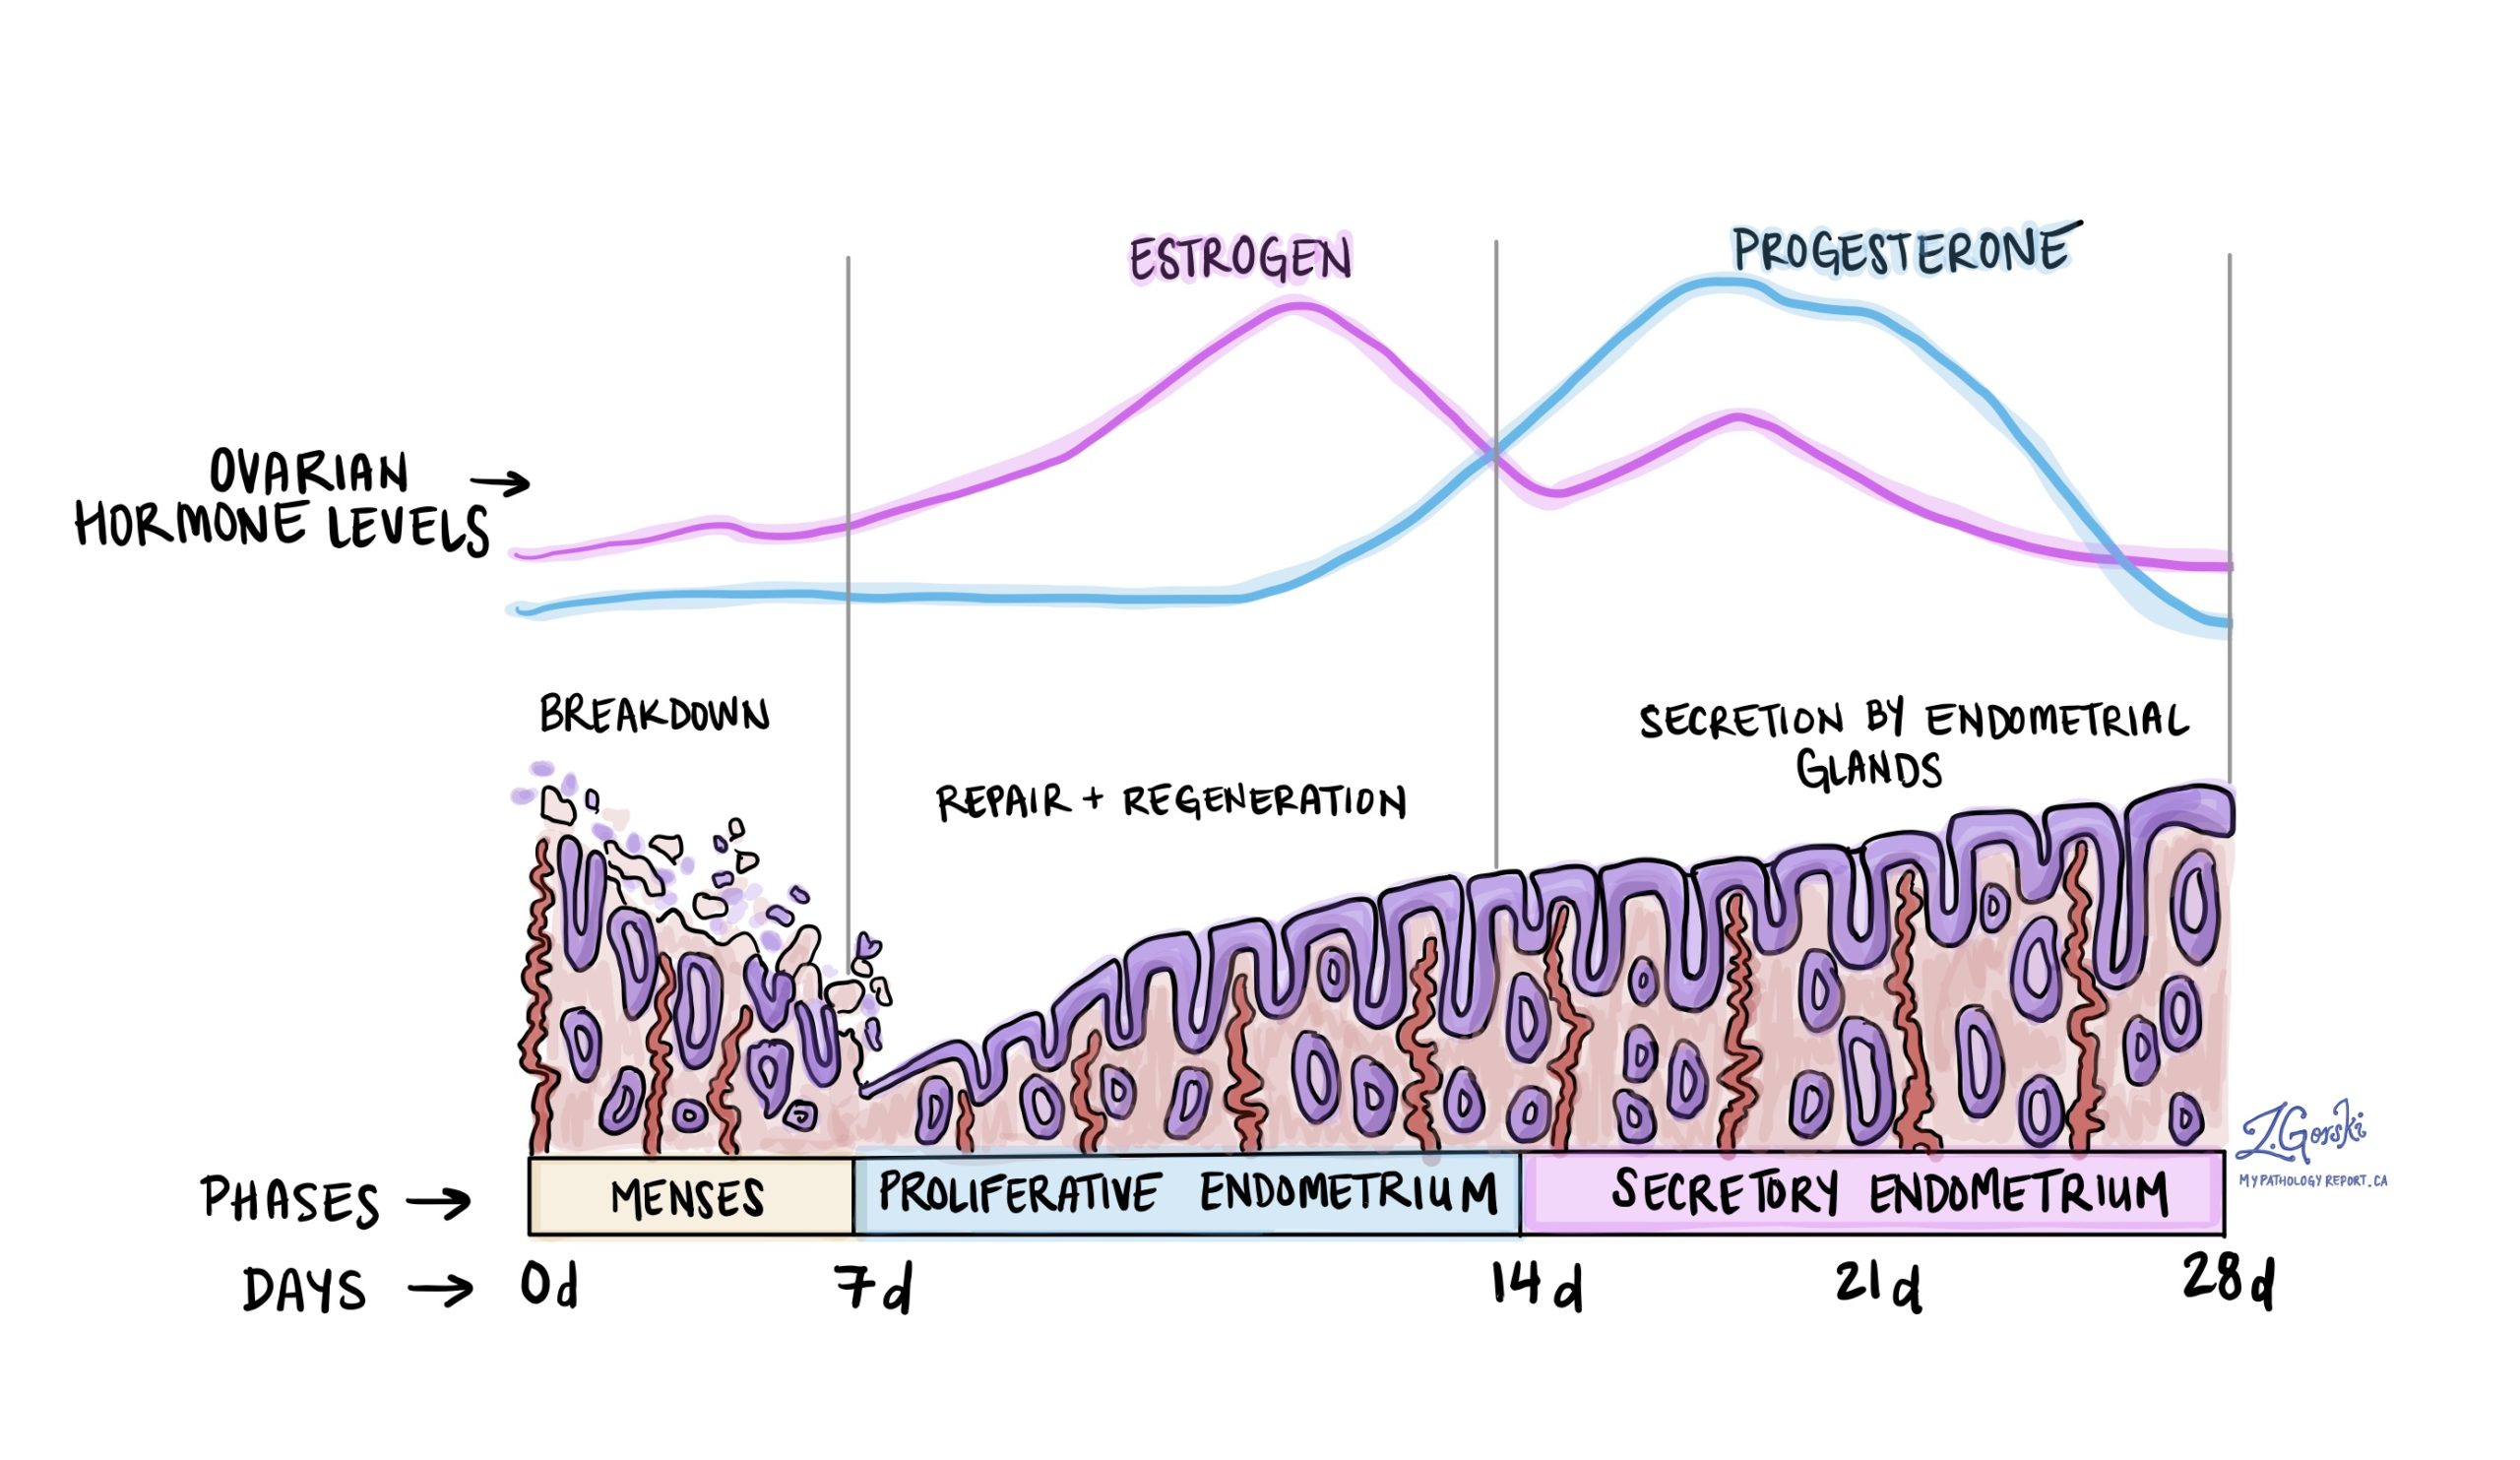
Secretory endometrium describes the normal appearance of the lining of the uterus during the second half of the menstrual cycle, after an egg has been released. The lining is called the endometrium. “Secretory” refers to the nourishing fluid the glands begin producing at this stage, which would support an embryo if pregnancy occurred.
This is a normal finding, not a disease. It is not cancer, and it is not precancerous. It also carries one piece of information nothing else on the report can give: these changes appear only under the influence of progesterone, and progesterone is produced only after ovulation. A secretory lining therefore confirms that you ovulated in that cycle.
This article will help you understand what the term means on your pathology report and how to read it in your own situation.
Why was my endometrium sampled?
The lining of the uterus is sampled by an endometrial biopsy, a brief clinic procedure using a thin flexible tube, or by a dilation and curettage. It may also be examined in a uterus removed at surgery. Common reasons for sampling include:
- Abnormal uterine bleeding — Heavy, prolonged, or irregular bleeding, or bleeding between periods.
- Bleeding after menopause — Any bleeding after menopause is investigated, whatever the eventual cause.
- Difficulty becoming pregnant — The lining is examined to see whether it is responding to hormones as expected.
- Follow-up of a previous finding — Confirming that endometrial hyperplasia has resolved after treatment.
- Investigation of a polyp — An endometrial polyp or an endocervical polyp seen on imaging or at hysteroscopy.
What does secretory endometrium look like under the microscope?
Secretory endometrium is the lining of the uterus after ovulation, changed by progesterone from a growing tissue into one prepared to receive an embryo. The appearance shifts over the roughly two weeks between ovulation and a period, and the pathologist looks for the following features.
- Clear droplets beneath the nuclei — In the first days after ovulation, small clear spaces appear underneath the nuclei of the cells lining the glands. These are the earliest reliable microscopic signs that ovulation has occurred.
- Coiled glands with secretions — The endometrial glands become long, twisted, and saw-toothed in outline, and their centers fill with the fluid they are producing.
- Swollen supporting tissue — The tissue between the glands becomes loose and swollen with fluid in the middle of this phase.
- Changes around blood vessels — Later in the phase, the supporting tissue around small spiral-shaped blood vessels enlarges and becomes pale, a change called predecidual reaction. This tissue becomes the decidua of pregnancy.
- Few dividing cells — Unlike the first half of the cycle, when the lining is rebuilding, cell division largely stops once progesterone takes over.
What does this finding mean in my situation?
Secretory endometrium is always a normal appearance, but whether it is the expected appearance depends on your circumstances.
- Before menopause, sampled in the second half of the cycle — Exactly what should be found, and confirmation that you ovulated that cycle.
- Before menopause, sampled in the first half of the cycle — Suggests the timing was different from what was assumed, either because ovulation came earlier than expected or because the cycle dates were uncertain.
- While taking progestin treatment — Progestin medications, including the hormonal IUD, produce secretory-type changes. The report describes how your lining is responding, which helps your doctor judge whether the treatment is working.
- After menopause — Unexpected without a source of progesterone, combined hormone therapy is the usual explanation. If you are not taking hormones, ask your doctor about this.
What does a post-ovulation day in my report mean?
Because the lining changes in a fairly predictable sequence after ovulation, a pathologist can estimate how many days have passed since an egg was released. This estimate is called the post-ovulation day, and you may see it written in your report. It is sometimes called endometrial dating.
The role of this estimate has changed, and it is worth knowing why. It was once used routinely in fertility investigation, on the theory that a lining lagging behind the expected day indicated a hormone problem. Large studies since then have not supported that use. Different pathologists dating the same slide often disagree, and the same person can date differently in different cycles. In one large trial, roughly half of biopsies from women with no fertility problems at all were reported as out of phase. Professional fertility societies no longer recommend endometrial dating as part of a fertility evaluation.
What the finding still tells you is simpler and more reliable. Secretory changes confirm that ovulation occurred. That information is useful, and it does not depend on pinpointing the exact day.
How is this different from other descriptions of the endometrium?
Pathologists use several terms to describe the lining, and most describe normal states rather than diseases. Your report may use any of the following.
- Proliferative endometrium — Normal, first half of the cycle, before ovulation. Proliferative endometrium shows straight, evenly spaced glands and active cell division.
- Secretory endometrium — Normal, second half of the cycle, after ovulation. Coiled glands producing secretions.
- Atrophic endometrium — A thin, inactive lining, and the expected finding after menopause. Atrophic endometrium reflects the absence of both hormones.
- Disordered proliferative endometrium — Irregular, unevenly spaced glands reflecting estrogen without progesterone. Disordered proliferative endometrium is not precancerous.
- Endometrial hyperplasia — Glands that have become genuinely crowded. This one is treated and followed.
What other findings may be described in the report?
Secretory endometrium is often reported alongside other findings from the same sample.
- Endometrial polyp — A benign overgrowth of the lining and a common cause of abnormal bleeding.
- Breakdown and bleeding — Areas where the lining is shedding, which may explain the symptoms.
- Chronic inflammation — If plasma cells are present, the report may also diagnose chronic endometritis.
- Negative for hyperplasia and malignancy — A standard phrase meaning the pathologist looked for crowded glands and for cancer and found neither.
- Sample adequacy — The report may say the sample was scant or fragmented. This may mean a repeat sample is needed to be confident nothing was missed.
What happens next?
A report of secretory endometrium alone requires no treatment and no follow-up in its own right. What happens next depends on why the sample was taken. Points your doctor may raise include:
- Looking elsewhere for a cause — If you were investigated for bleeding and the lining is normal, the bleeding has another explanation. Fibroids, polyps, adenomyosis, and hormonal causes are all possibilities.
- Fertility investigation — A secretory lining confirms ovulation, which is one question answered. Other parts of a fertility assessment, such as hormone testing and imaging of the tubes, address different questions.
- Reviewing hormone treatment — If you are taking progestin or combined hormone therapy, the appearance of the lining may inform whether to continue or adjust it.
- Repeating the sample — If the sample was scant or the bleeding continues, your doctor may arrange a repeat biopsy or a hysteroscopy.
Questions to ask your doctor
- Is this a normal finding for where I was in my cycle?
- Does this confirm that I ovulated?
- My report gives a post-ovulation day. What does that mean for me?
- Does this finding explain my bleeding, or should we look elsewhere?
- I have gone through menopause. Should a secretory lining be there?
- Is this the effect of the hormone treatment I am taking?
- Was the sample adequate, or should it be repeated?
- Did you report a polyp or any other finding?
- Does my report say negative for hyperplasia and malignancy?
- What are the next steps in my fertility assessment?
- Do I need any treatment or follow-up?
- What symptoms should prompt me to contact you?
Related articles on MyPathologyReport.com
We are proud to partner with:


🔍 Search MyPathologyReport
Type what you see on your report — for example a diagnosis or test name