

Section Editor: Trevor Flood MD FRCPC
October 9, 2026
Urothelial carcinoma is a type of cancer that starts from the urothelial cells that line the inside of the urinary tract. Most urothelial carcinomas start in the bladder, and it is by far the most common type of bladder cancer. It can also start in the lining of the kidney, the ureters that carry urine down to the bladder, or the urethra.
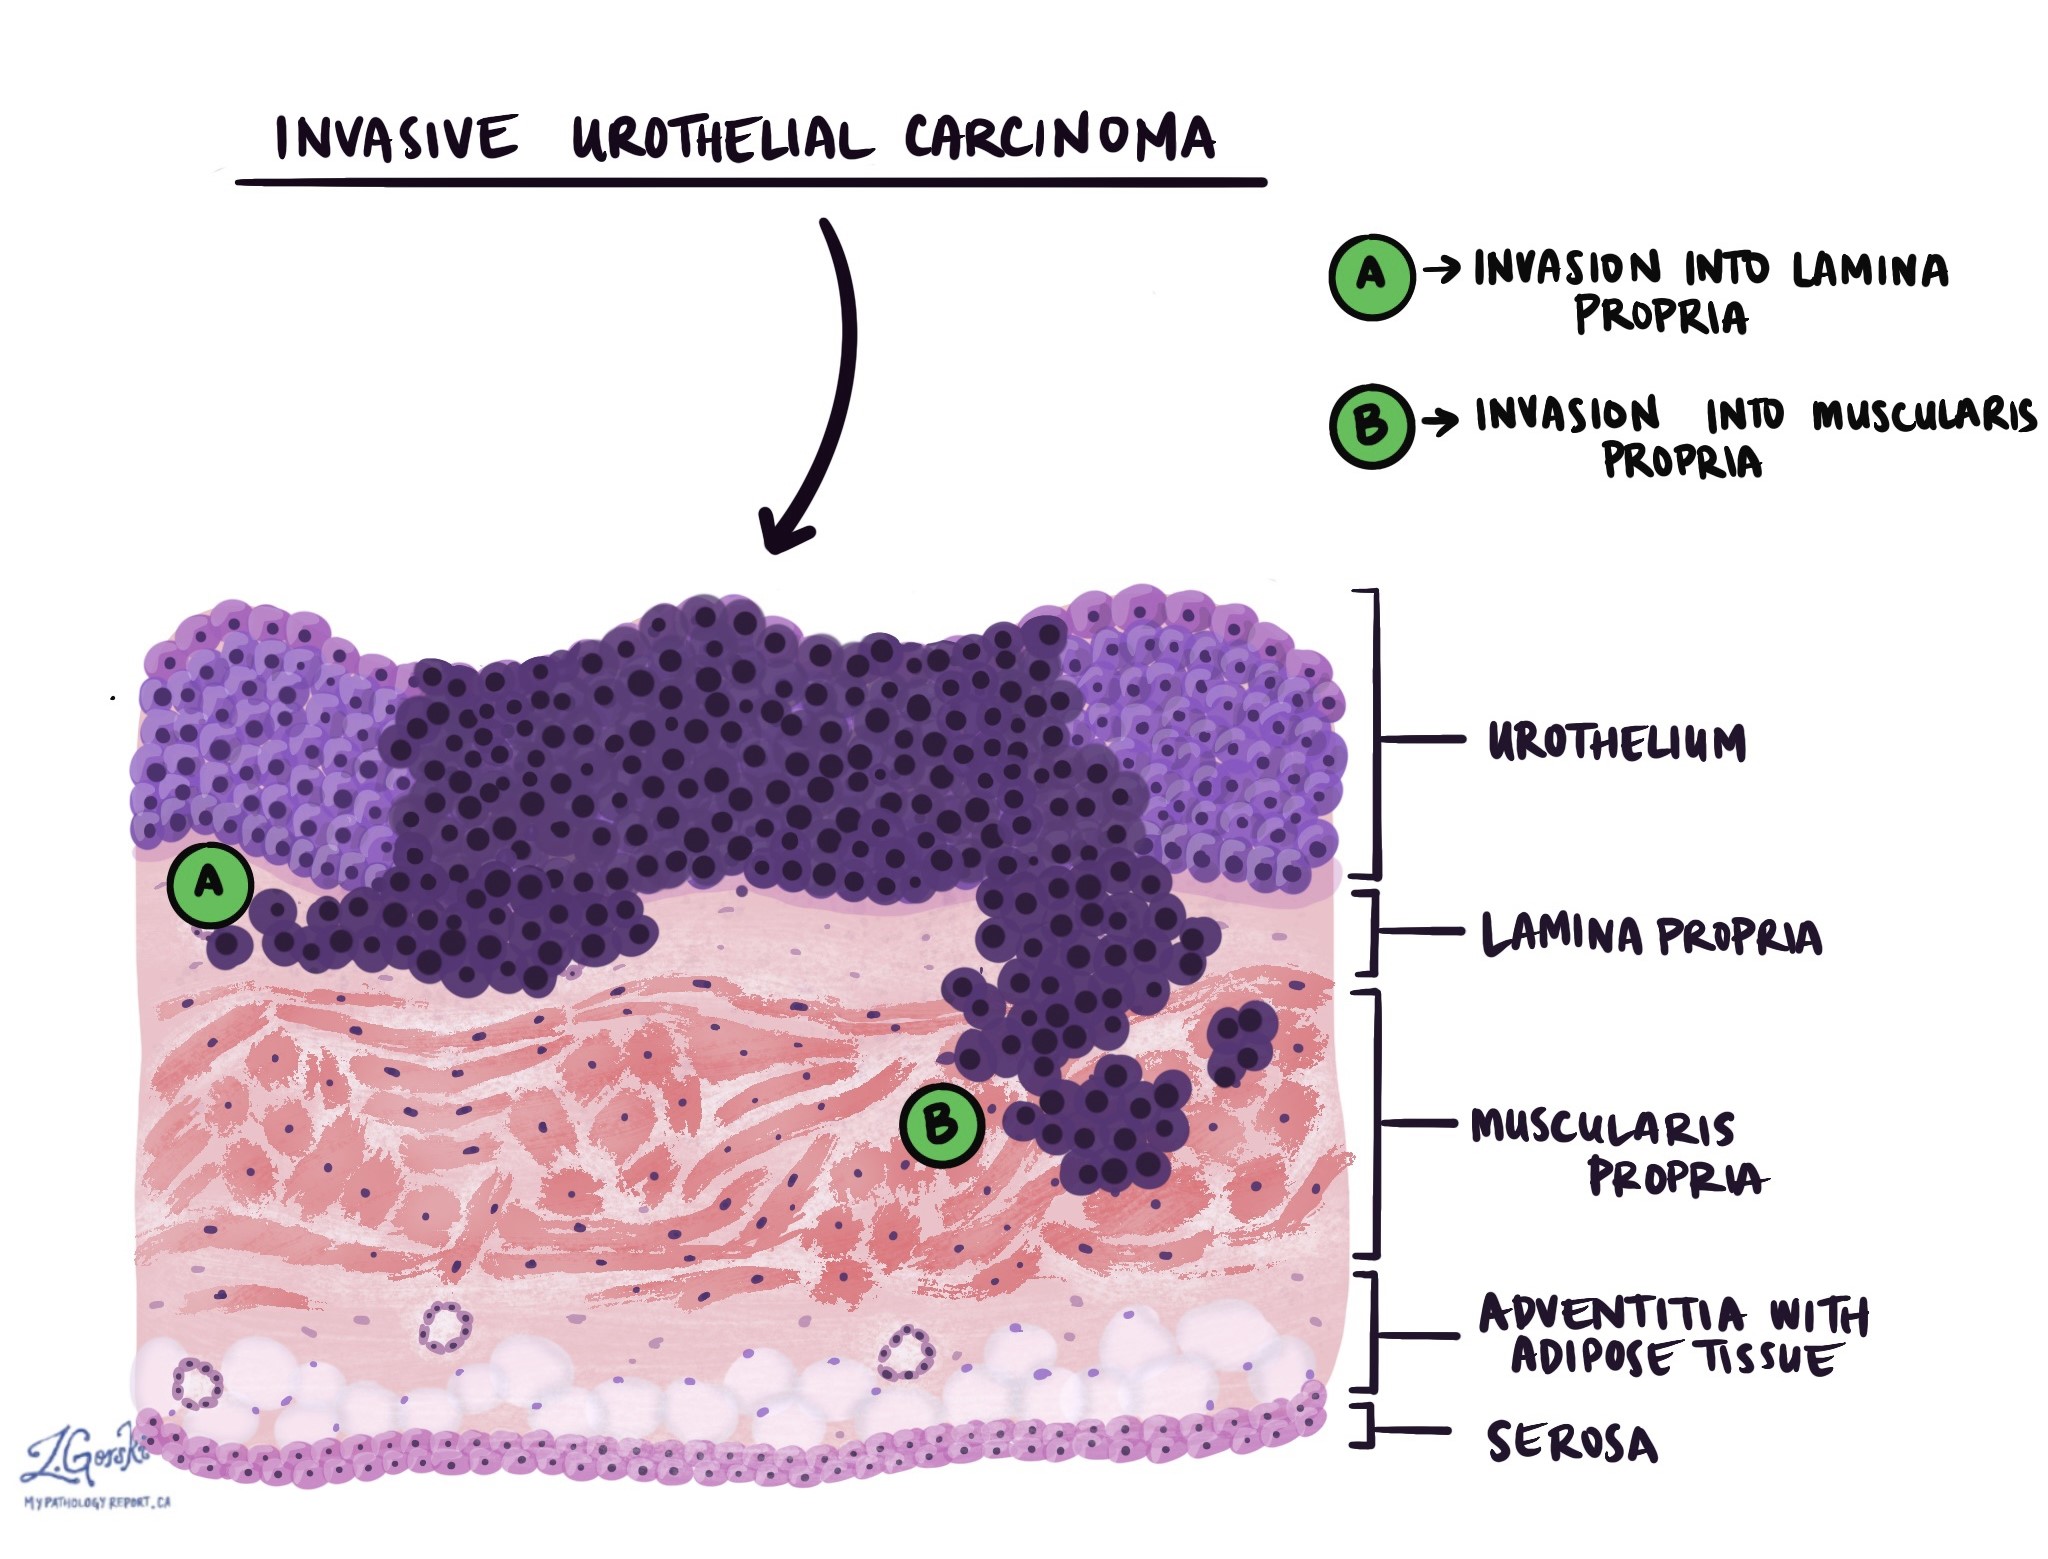
Urothelial carcinoma can grow in two ways. In the non-invasive form, cancer cells stay within the lining, either as finger-like growths (papillary urothelial carcinoma) or as a flat layer (urothelial carcinoma in situ). In the invasive form, cancer cells grow beyond the lining into the deeper layers of the wall. This is what your report means when it says “invasive urothelial carcinoma.”
This article explains how doctors diagnose invasive urothelial carcinoma and what the subtype, grade, depth of invasion, margins, lymph nodes, biomarkers, and stage in your pathology report mean. Most of the article focuses on the bladder, where most of these cancers start.
Who gets urothelial carcinoma?
Urothelial carcinoma of the bladder is mainly a disease of older adults, and the typical age at diagnosis is in the early 70s. It is about four times more common in men than in women. It is uncommon before the age of 40.
What causes urothelial carcinoma?
Smoking is the most important cause of urothelial carcinoma, because chemicals from tobacco smoke are filtered into the urine, where they damage the lining of the bladder. Long-term exposure to certain industrial chemicals, such as aromatic amines once used in dye and rubber manufacturing, also increases risk. Other causes include arsenic in drinking water and herbal products containing aristolochic acid.
Long-term bladder irritation, for example from a chronic infection with the parasite Schistosoma haematobium, also raises the risk. Earlier treatment with radiation to the pelvis or with the chemotherapy drug cyclophosphamide is another known cause.
A small number of urothelial carcinomas are linked to an inherited condition called Lynch syndrome. This link is strongest for tumors that start in the kidney or ureter, and it is the reason some reports include mismatch repair testing.
What are the symptoms?
The most common symptom of urothelial carcinoma is blood in the urine, which is usually painless and may come and go. Some people notice the blood themselves, while in others it is found only on a urine test. Other symptoms include burning during urination, needing to urinate often or urgently, and pain in the side or lower back if the tumor blocks the flow of urine.
How is the diagnosis made?
The diagnosis of urothelial carcinoma usually begins after blood is found in the urine. A doctor may send a urine sample for cytology, a test in which a pathologist looks for cancer cells. Our article on cytology explains this test.
A urologist then uses a thin camera to look inside the bladder in a procedure called cystoscopy. If a tumor is seen, it is removed through the urethra in a procedure called a transurethral resection of bladder tumor, or TURBT. Our article on the TURBT pathology report explains the procedure and what pathologists examine.
Under the microscope, a pathologist confirms that the tumor is a urothelial carcinoma and decides how deeply it has grown into the wall of the bladder. The pathologist also reports whether the thick muscle layer of the bladder wall, called the muscularis propria, is present in the sample. This matters because a tumor can be shown as muscle-invasive only if the tissue removed includes muscle.
Your TURBT report will describe the muscle layer of the bladder wall in one of these ways:
- Not identified. No muscle was included in the sample, so the pathologist cannot tell whether the cancer has reached it. If the tumor is high grade or invasive, a second TURBT is often done.
- Present, negative for tumor. The sample included muscle, and no cancer cells were seen.
- Present, involved by tumor. Cancer cells have grown into the muscle, which means the cancer is muscle-invasive.
- Cannot be determined. The pathologist could not tell with certainty, often because the tissue was damaged during removal.
Once muscle-invasive urothelial carcinoma is confirmed, CT or MRI scans are used to look for spread to lymph nodes and other organs.
What are the different types?
Most invasive urothelial carcinomas are the conventional type, which means the tumor cells look like typical urothelial carcinoma under the microscope. The World Health Organization (WHO) classification, 5th edition (2022), and the College of American Pathologists (CAP) protocol also recognize several subtypes. Older reports may call these subtypes “variants.”
Many invasive tumors contain a mixture of conventional and subtype areas. For this reason, the pathologist may list each subtype and the percentage of the tumor it represents. The subtypes most likely to appear on a report are:
- Micropapillary. The tumor cells form tiny clusters that sit in small empty spaces in the tissue. The micropapillary subtype often spreads to lymph nodes, so your team may recommend earlier or more extensive surgery.
- Nested. The tumor cells grow in small or large rounded groups called nests. Because the cells can look deceptively bland, this subtype can be hard to recognize on a small biopsy, but it behaves like other invasive urothelial carcinomas.
- Tubular and microcystic. The tumor cells form small tubes or tiny fluid-filled spaces. Like the nested subtype, it can look deceptively bland under the microscope.
- Plasmacytoid. The tumor cells resemble plasmacytoid cells, a type of immune cell, and spread individually through the tissue. This subtype often spreads along the abdominal lining and is usually found at an advanced stage.
- Sarcomatoid. Some tumor cells become long and thin, like sarcoma cells. The sarcomatoid subtype tends to grow quickly and is often found at an advanced stage.
- Lymphoepithelioma-like. The tumor cells are surrounded by large numbers of immune cells called lymphocytes. When the whole tumor has this pattern, it may respond better to chemotherapy than conventional urothelial carcinoma.
- Other uncommon subtypes. These include the giant cell, poorly differentiated, lipid-rich, and clear cell subtypes, each named for how the tumor cells look. Each is rare, and your team can explain what yours means for your care.
Some urothelial carcinomas also show divergent differentiation, which means part of the tumor looks like a different kind of cancer. The most common form is squamous differentiation, where some cells look like squamous cells, and the next most common is glandular differentiation, where some cells form glands. Rarer forms are trophoblastic and Müllerian differentiation. Divergent differentiation does not change the diagnosis of urothelial carcinoma, but it is reported because it can affect how the tumor responds to treatment.
Histologic grade
Urothelial carcinoma is graded based on how different the tumor cells look from normal urothelial cells. The grade helps predict tumor behavior and is one of the findings your team uses to plan treatment. There are two grades:
- Low grade. The tumor cells look only slightly different from normal urothelial cells. Low-grade tumors grow slowly, are usually non-invasive, and rarely spread, although they often come back in the bladder.
- High grade. The tumor cells look very different from normal urothelial cells. High-grade tumors are more likely to invade the bladder wall and to spread, and most invasive urothelial carcinomas are high grade.
All of the subtypes described above, and tumors with divergent differentiation, are considered high grade, even when the cells look bland under the microscope. If your tumor contains both low-grade and high-grade areas, it is graded as high grade when the high-grade areas make up 5% or more of the tumor.
Depth of invasion
Depth of invasion describes how far urothelial carcinoma has grown into or through the bladder wall. It is the most important finding in your report because it determines the tumor stage and the treatment you are likely to receive. The bladder wall has several layers, and your report will name the deepest layer containing cancer cells.
- Lamina propria. The lamina propria is the thin layer of connective tissue just below the lining. Cancer that has grown into this layer, but no deeper, is called non-muscle-invasive bladder cancer. Some reports also describe how much of the lamina propria is involved, because more extensive invasion is linked to a higher risk of the cancer progressing.
- Muscularis propria. This is the thick muscle layer of the bladder wall. Cancer that has grown into this layer is called muscle-invasive bladder cancer, and it is usually treated with chemotherapy and surgery to remove the bladder, or with chemotherapy and radiation.
- Perivesical tissue. This is the fat around the bladder. Your report may say whether the cancer in the fat can be seen only with a microscope or with the naked eye.
- Adjacent organs. The cancer has grown directly into a nearby organ, such as the prostate, uterus, or vagina, or into the wall of the pelvis or abdomen.
Your report may also mention urothelial carcinoma in situ in the lining around the tumor. This flat, non-invasive form of the cancer is common alongside invasive tumors. It matters because it can come back in other parts of the bladder lining.
Lymphovascular invasion
Lymphovascular invasion means cells from the urothelial carcinoma are seen inside a small blood vessel or a lymphatic channel. Your report may call this “lymphatic and/or vascular invasion,” and it is reported as present, not identified, or cannot be determined. When it is present, the cancer is more likely to have spread to lymph nodes or other organs, even if the tumor has not grown deeply.
Treatment effect
Many people with muscle-invasive urothelial carcinoma receive chemotherapy, sometimes with immunotherapy, before surgery to remove the bladder. In these cases, your report on the bladder may describe how much the tumor responded to that treatment. Some reports use a scale from complete response (meaning no cancer cells remain) to weak or no response. A complete response is linked to a much better outlook. If you did not receive treatment before surgery, your report may say there was no known treatment before surgery.
Margins
When the bladder is removed in an operation called a cystectomy, the pathologist examines the cut edges, or margins, of the tissue removed with the urothelial carcinoma. Pathologists usually examine the ends of the ureters, the urethra, and the soft tissue around the bladder. Our article on the radical cystectomy pathology report describes this operation.
- Negative margin. No cancer cells are seen at any cut edge, which suggests the tumor was completely removed. Some reports also give the distance between the cancer and the closest margin.
- Positive margin for invasive cancer. Invasive cancer cells are seen at a cut edge, which suggests some cancer may remain in the body. Your team may consider additional treatment, such as radiation or chemotherapy.
- Positive margin for carcinoma in situ. Non-invasive cancer cells are seen in the lining at a cut edge, usually at the end of a ureter or the urethra. This is linked to a higher chance of the cancer coming back in the remaining lining, which is checked during follow-up.
A TURBT removes the tumor in small pieces, so margins are not usually reported on a TURBT specimen.
Lymph nodes
Urothelial carcinoma of the bladder can spread to lymph nodes in the pelvis, small immune organs that filter fluid from tissues. Surgeons usually remove these lymph nodes during a cystectomy. Your report will say how many lymph nodes were examined and how many contain cancer.
Some reports also give the size of the largest cancer deposit in a lymph node. Your report may also mention extranodal extension, meaning cancer cells have broken through the lymph node’s outer capsule into the surrounding tissue. Cancer in more lymph nodes, larger deposits, and extranodal extension are all linked to a higher chance of the cancer coming back. When cancer is found in lymph nodes, treatment after surgery is usually considered.
Biomarker and molecular testing
Biomarker testing for urothelial carcinoma looks for features of the cancer cells that can guide treatment, especially when the cancer has spread or comes back after surgery. These tests aren’t included in every report, and many are done only when the cancer is advanced. They may be performed on the TURBT, the cystectomy specimen, or a biopsy of a site of spread.
FGFR3
FGFR3 is a gene that makes a protein involved in cell growth. Changes in FGFR3, either a mutation or a fusion with another gene, are found in many urothelial carcinomas. Molecular testing, such as next-generation sequencing (NGS), is used, and results are reported as “detected” or “not detected.”
If an FGFR3 change is detected and the cancer is advanced, it can make a person eligible for erdafitinib. The FDA granted full approval to erdafitinib in January 2024 for adults with advanced urothelial carcinoma and certain FGFR3 changes, after at least one earlier treatment. A “not detected” result is common and means this drug isn’t an option, but other treatments remain available.
HER2
HER2 is a protein on the surface of some cancer cells that helps them grow. It is tested by immunohistochemistry, and the result is scored from 0 to 3+. A score of 3+ means the cancer cells make a large amount of HER2, while a score of 0 or 1+ means they make little or none.
For advanced cancer with a HER2 score of 3+, trastuzumab deruxtecan may be an option. The FDA granted accelerated approval in April 2024 for advanced solid tumors with a HER2 score of 3+, after earlier treatment, regardless of where the cancer started. A score of 2+ is an in-between result, and your oncologist can explain what it means in your situation.
PD-L1
PD-L1 is a protein that some cancer cells use to hide from the immune system. Doctors test it by immunohistochemistry, and the result is usually reported as a combined positive score (CPS) or as positive or negative. For most current immunotherapy treatments for urothelial carcinoma, a PD-L1 result is not required. For example, the combination of enfortumab vedotin and pembrolizumab was effective regardless of the PD-L1 result in the study that led to its approval. Our article on PD-L1 testing in cancer explains how the test works.
Mismatch repair proteins
Mismatch repair proteins fix mistakes that happen when a cell copies its DNA. Testing looks for four proteins called MLH1, PMS2, MSH2, and MSH6. It is done most often on tumors from the kidney or ureter, because of their link to Lynch syndrome.
- Intact, retained, or no loss of expression. All four proteins are present. This is the normal result, making Lynch syndrome unlikely.
- Loss of expression. One or more proteins are missing. This result does not confirm Lynch syndrome, but it warrants referral for genetic counseling and a blood test. Tumors with this result may also respond well to immunotherapy.
Our article on mismatch repair across cancer types explains these results in more detail. For more information on tumor testing, visit our Biomarkers and Genetic Testing section.
Pathologic stage (pTNM)
The pathologic stage for urothelial carcinoma of the bladder is assigned using the TNM system from the AJCC Cancer Staging Manual, 8th edition. The tumor stage (pT) describes how deeply the cancer has grown, and the nodal stage (pN) describes spread to lymph nodes. Imaging, rather than the pathology report, usually determines spread to distant organs (M).
Tumor stage (pT)
- pTa. The tumor is non-invasive and papillary, meaning it grows as finger-like projections that have not invaded below the lining.
- pTis. The tumor is flat, non-invasive urothelial carcinoma in situ.
- pT1. The tumor has grown into the lamina propria but not into the muscle layer.
- pT2. The tumor has grown into the muscularis propria. It is pT2a if it involves only the inner half of the muscle and pT2b if it reaches the outer half.
- pT3. The tumor has grown through the muscle into the fat around the bladder. It is pT3a if the cancer in the fat is seen only with a microscope and pT3b if it can be seen with the naked eye.
- pT4. The tumor has grown into a nearby organ. It is pT4a if it involves the prostate, uterus, or vagina, and pT4b if it involves the wall of the pelvis or abdomen.
Nodal stage (pN)
- pN0. No cancer was found in the examined lymph nodes.
- pN1. Cancer was found in a single pelvic lymph node.
- pN2. Cancer was found in more than one lymph node in the pelvis.
- pN3. Cancer was found in lymph nodes along the common iliac arteries, higher up where the large blood vessels to the legs divide.
If no lymph nodes were removed, as is usual for a TURBT, your report may say that the nodal stage was not assigned. Urothelial carcinomas that start in the kidney or ureter are staged with slightly different definitions because these organs have thinner walls than the bladder. Your doctors combine the pathologic stage with your scans to give an overall stage from 0 to IV.
What is the prognosis?
The prognosis for urothelial carcinoma depends mostly on how deeply the cancer has grown and whether it has spread. The figures below describe large groups of people with bladder cancer, most of whom had urothelial carcinoma.
- Non-invasive cancer limited to the lining. About 98 in 100 people are alive five years after diagnosis. About half of all bladder cancers are found at this stage.
- Cancer that has invaded the bladder wall but not spread. About 73 in 100 people are alive five years after diagnosis, and about 27 in 100 are not.
- Cancer that has spread to nearby lymph nodes or tissues. About 42 in 100 people are alive five years after diagnosis.
- Cancer that has spread to distant organs. About 10 in 100 people are alive five years after diagnosis.
These numbers are averages, and many of the people they describe were treated before the newest drugs became available. They cannot tell you what will happen to you. Features in your report that are linked to a higher chance of the cancer coming back or spreading include:
- Deep invasion. Cancer that has reached the muscle layer, the fat around the bladder, or a nearby organ.
- Lymph node spread. Cancer in lymph nodes, especially in several nodes or with extranodal extension.
- Lymphovascular invasion. Cancer cells inside small vessels, which can carry them to other parts of the body.
- Certain subtypes. The micropapillary, plasmacytoid, and sarcomatoid subtypes are more often found at an advanced stage.
- A positive margin. Some cancer cells may remain in the body after surgery.
- Little response to treatment before surgery. A weak response is linked to a higher chance of the cancer coming back.
What happens after the diagnosis?
After a diagnosis of urothelial carcinoma, your care team uses the depth of invasion, grade, and other findings in your report to plan treatment. The team often includes a urologist, a medical oncologist, and a radiation oncologist. Cancer treatment that has not reached the muscle is very different from treatment for muscle-invasive cancer.
- Non-muscle-invasive cancer. The TURBT itself may remove the cancer completely. Medicine is often placed directly into the bladder through a catheter to lower the chance of the cancer coming back. The most common is BCG, a weakened bacterium that stimulates the immune system. Regular cystoscopy is needed because these cancers often come back.
- Muscle-invasive cancer. Treatment usually combines chemotherapy, sometimes with immunotherapy, and surgery to remove the bladder. In March 2025, the FDA approved durvalumab with chemotherapy before surgery, followed by durvalumab after surgery. In November 2025, the FDA approved enfortumab vedotin with pembrolizumab before and after surgery for people who cannot receive cisplatin.
- Bladder-sparing treatment. For some people, chemotherapy combined with radiation is an alternative to removing the bladder.
- Treatment after surgery. For people at high risk of the cancer coming back after surgery, the FDA approved nivolumab as treatment after surgery in August 2021.
- Advanced cancer. In December 2023, the FDA approved enfortumab vedotin with pembrolizumab as a first treatment for advanced urothelial carcinoma. The targeted drugs described in the biomarker section may be options later, for tumors with the matching test result.
Approval and access to these drugs differ by country, and your care team can explain what applies where you live. Follow-up includes regular cystoscopy, urine tests, and scans, depending on the stage of the cancer and the treatment you received.
Questions to ask your doctor
- How deeply did the cancer grow into the bladder wall?
- Was muscle included in my TURBT sample, and do I need a second TURBT?
- Is my cancer low grade or high grade?
- Does my tumor have any subtypes, such as micropapillary or plasmacytoid, and what percentage of the tumor do they make up?
- Was carcinoma in situ found in the lining around the tumor?
- Was lymphovascular invasion found?
- Were the margins negative, including the ends of the ureters and the urethra?
- How many lymph nodes were examined, and did any contain cancer?
- What is the stage of my cancer?
- Should my tumor be tested for FGFR3, HER2, or other biomarkers?
- Would treatment before surgery be helpful for me?
- Is bladder-sparing treatment an option for me?
- How often will I need cystoscopy and scans after treatment?
Related articles on MyPathologyReport.com
- Papillary urothelial carcinoma
- High-grade papillary urothelial carcinoma
- Low-grade papillary urothelial carcinoma
- Urothelial carcinoma in situ
- Urothelial papilloma
- Understanding your TURBT pathology report
- Understanding your radical cystectomy pathology report
- PD-L1 testing in cancer
- Muscularis propria
We are proud to partner with:


🔍 Search MyPathologyReport
Type what you see on your report — for example a diagnosis or test name