

Section Editor: Jason Wasserman MD PhD FRCPC
November 6, 2026
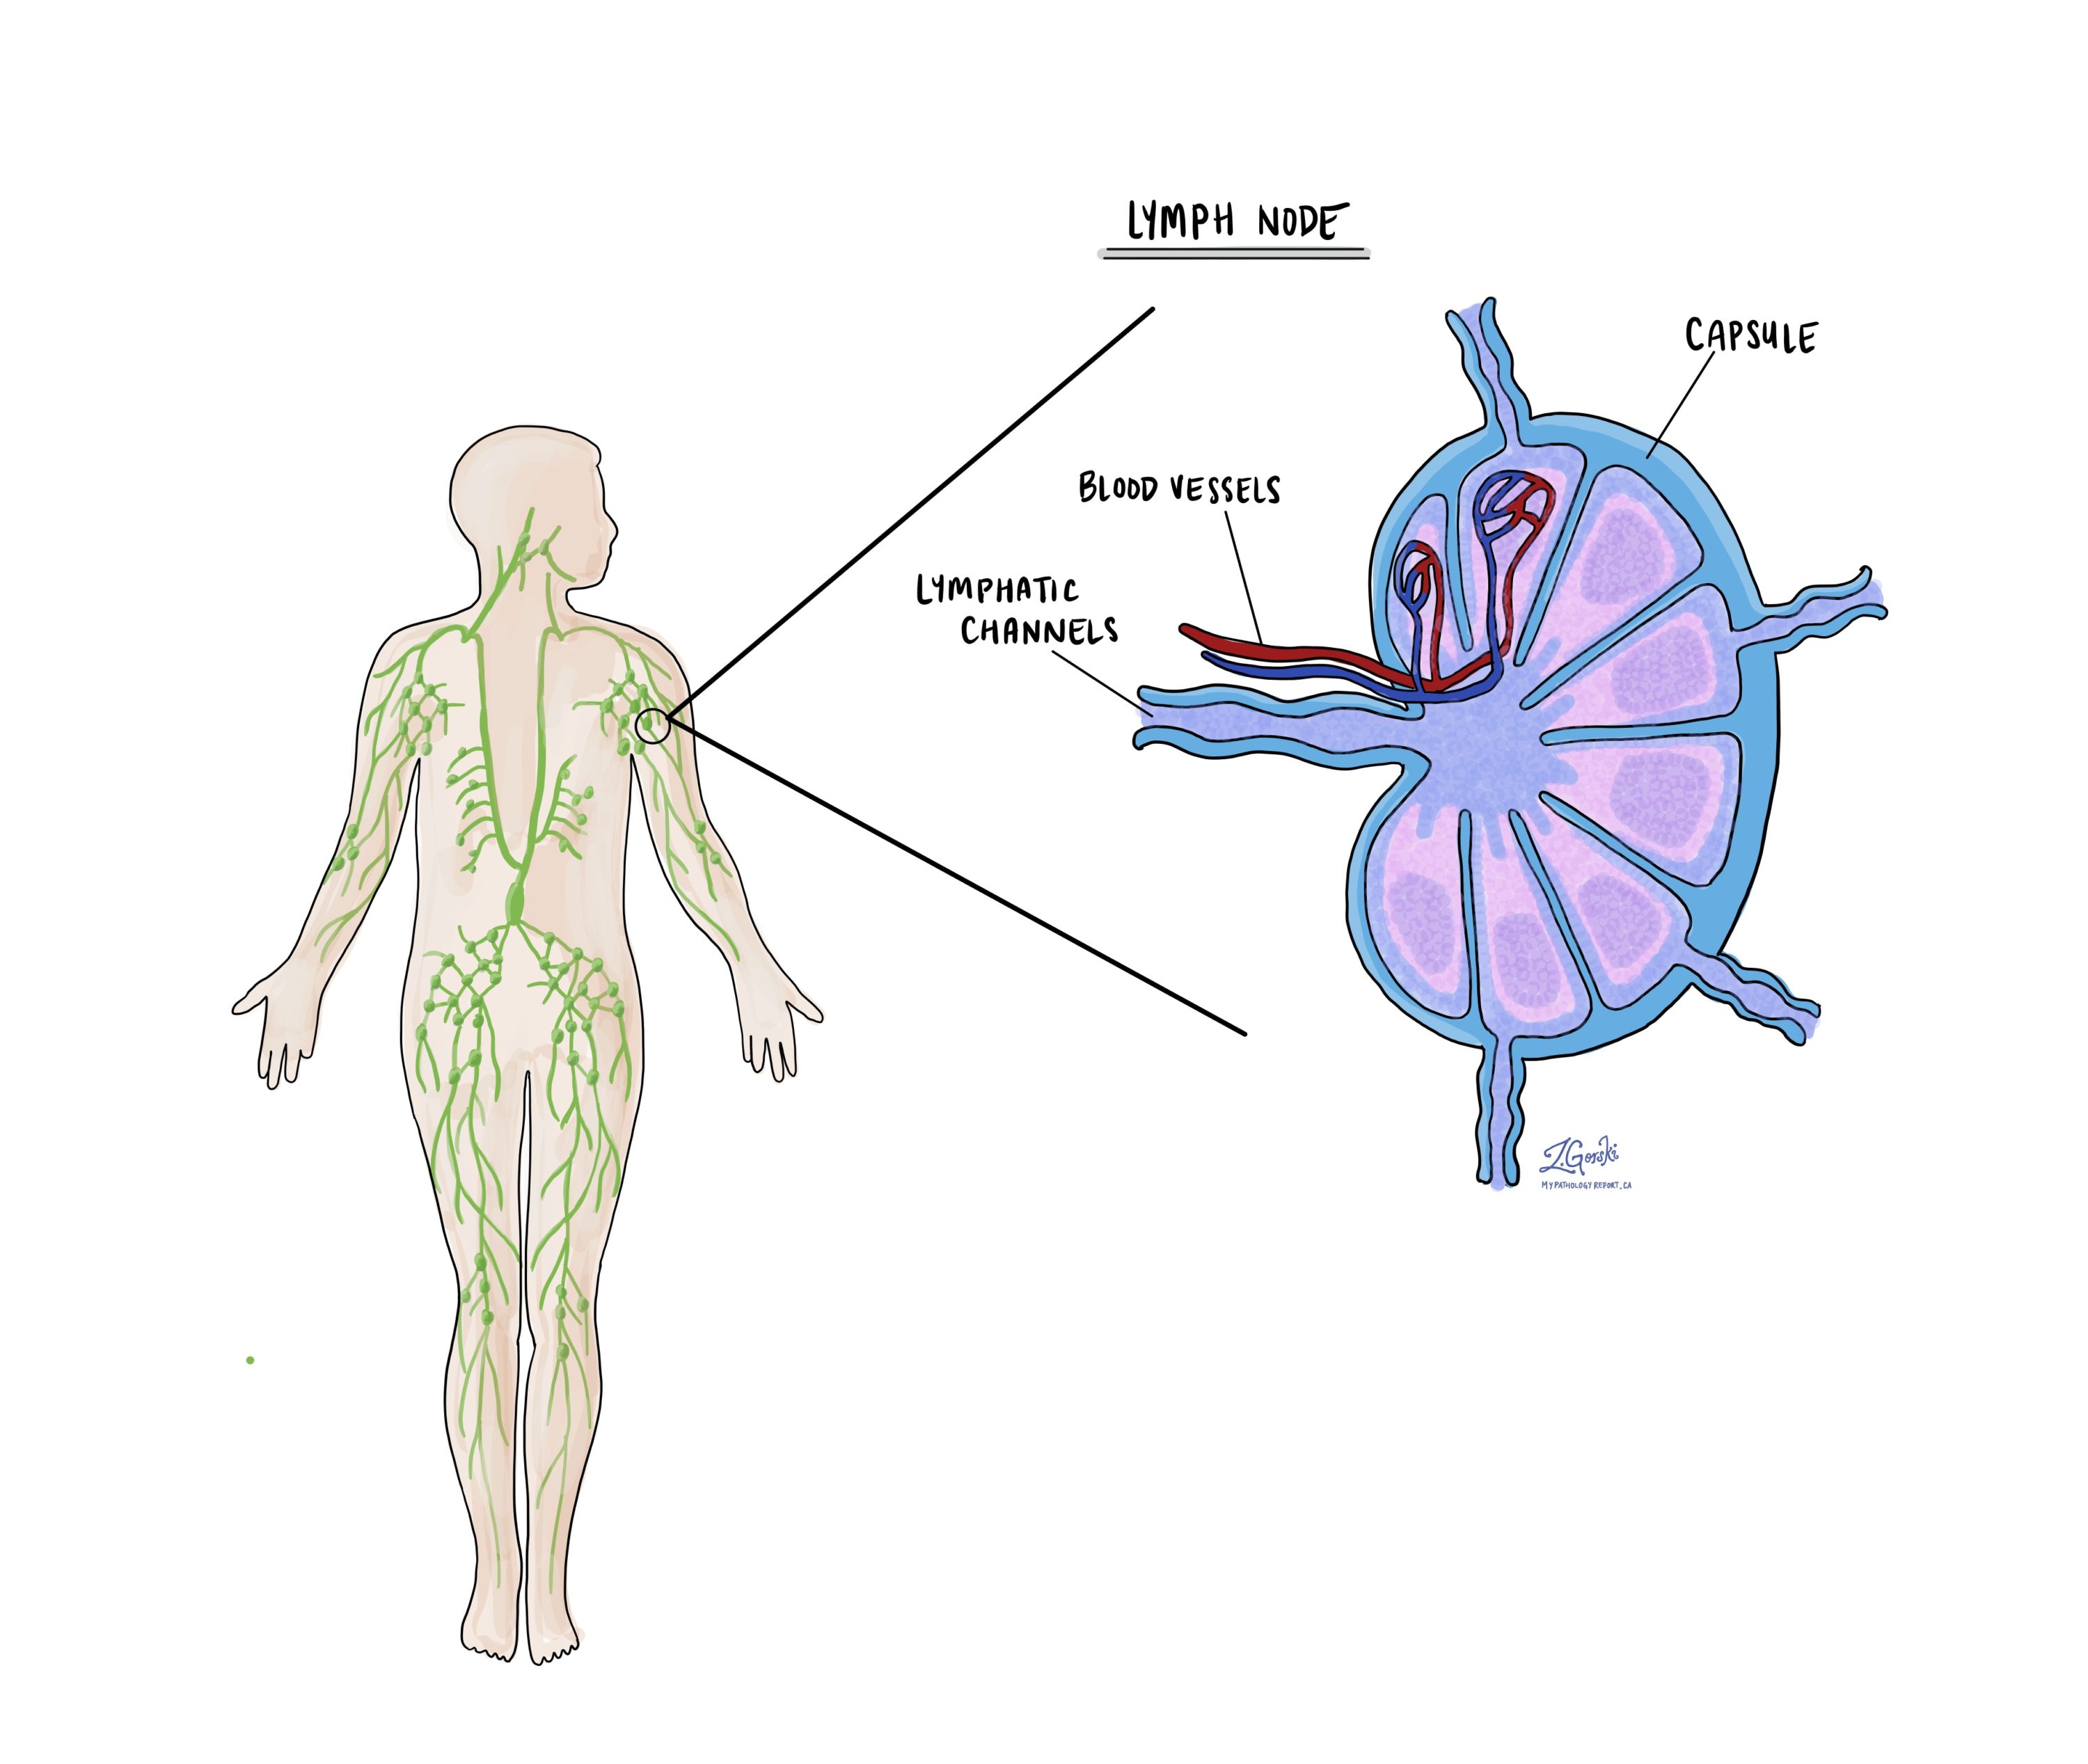
Lymph nodes are small, bean-shaped organs that filter tissue fluid and help the body fight infection. Cancer cells can travel through lymphatic channels and settle in nearby lymph nodes. For that reason, lymph nodes are often removed during cancer surgery and examined by a pathologist. A lymph node may also be removed on its own when it is enlarged, and nobody yet knows why.
This article explains how to read the lymph node findings in your pathology report. It covers phrases such as “3 of 14 lymph nodes positive” and the size categories used for cancer in a lymph node. It also covers extranodal extension and how these results become the N stage. It also explains what a report means when the lymph node itself was the specimen.
What are lymph nodes, and why does the pathologist examine them?
Lymph nodes are part of the lymphatic system, a network of thin channels that drains fluid from every part of the body. Each organ drains to a predictable group of lymph nodes, called its regional lymph nodes. The breast drains mainly to the armpit, and the colon drains to nodes in the fat beside it. Our dictionary entry on lymph nodes describes their normal structure.
When a cancer spreads beyond where it started, the regional lymph nodes are often the first place it goes. Finding cancer cells in a lymph node is called a lymph node metastasis. Whether the lymph nodes contain cancer is one of the strongest predictors of prognosis for many cancers. It also helps your care team decide whether to consider treatment beyond surgery.
How do lymph nodes end up in a pathology report?
Lymph nodes can reach the lab in several ways, and how they were removed changes what the report can say. The specimen description at the top of your report usually names the method. The common routes are:
- Sentinel lymph node biopsy. The surgeon removes only the first one to a few lymph nodes that drain the tumor. These nodes are found by injecting a radioactive tracer, a blue dye, or both near the tumor. Our sentinel lymph node entry and our guide to the sentinel lymph node biopsy report explain this procedure in detail.
- Lymph node dissection. The surgeon removes a whole group of lymph nodes, such as the nodes in the armpit or the neck. A neck dissection is one example.
- Nodes removed with the tumor. In many operations, such as removing part of the colon, lymph nodes sit in the fat attached to the organ. The pathologist searches that fat for every node.
- Biopsy of a single enlarged node. The whole node may be removed, or a needle may sample it. A fine needle aspiration collects cells, and a core needle biopsy collects a thin strip of tissue.
Some sentinel node labels include a number, such as “Target count=4153,” or the words “hot” or “blue.” The count is the radioactivity the surgeon measured over that node with a handheld probe. It shows how the surgeon found the node, not whether it contains cancer. In one large melanoma study, the cancer was in a lower-count node in about 23% of patients with a positive sentinel node.
Sometimes no lymph nodes are removed. This can happen when the operation did not include the lymph nodes or when imaging showed no concern. In that situation, the pathology report will not describe lymph nodes, and the lymph node status comes from imaging or physical examination instead.
How do I read a lymph node count such as “3 of 14”?
Most reports give two lymph node numbers: how many nodes were examined, and how many contained cancer. These are written in several ways that mean the same thing. “3 of 14,” “3/14,” and “metastatic carcinoma in 3 of 14 lymph nodes” all mean that 14 nodes were examined and 3 contained cancer.
- Negative. No cancer was found in that lymph node. Reports may say “negative for malignancy,” “negative for tumor,” “no metastatic carcinoma,” or “0/1.” Patients often describe this as “the nodes were clean.”
- Positive. Cancer was found in the node. Reports may say “positive,” “involved,” or “metastatic carcinoma present.”
- Number examined. This is the total number of nodes the pathologist found and looked at under the microscope. It includes both the positive and the negative nodes.
Sentinel nodes are often reported one at a time. A report might list “Sentinel node #1: one lymph node negative for tumor (0/1)” and then the same line for node #2. Your doctor adds these together to get the total. Many cancer reports also include a summary line that gives the combined count for all lymph nodes.
Where the nodes came from also matters; a report may separate nodes by level or location, such as “level I axilla” or “right neck, level II.” The pattern of which groups contain cancer can change the stage for some cancers, particularly in the head and neck.
What does the size of the cancer in a lymph node mean?
When a lymph node contains cancer, the pathologist measures the largest single cluster of cancer cells in that node. This cluster is called a deposit. The pathologist measures only one continuous deposit, and does not add separate small clusters together. The deposit size places the lymph node finding into one of three categories.
- Isolated tumor cells. Single cancer cells or tiny clusters measuring 0.2 mm or less, or no more than about 200 cells in one section. They are often found only with special stains. For most cancers, a node with only isolated tumor cells is not counted as a positive node, and the stage is written pN0(i+).
- Micrometastasis. A deposit larger than 0.2 mm but no larger than 2 mm. In breast cancer, a node with only a micrometastasis is counted as positive and staged pN1mi.
- Macrometastasis. A deposit larger than 2 mm. This is what most people mean by cancer in a lymph node, and it is always counted as a positive node.
These cutoffs come from the AJCC Cancer Staging Manual, 8th edition, and the exact rules differ by cancer. Melanoma and Merkel cell carcinoma are the main exceptions. For those two cancers, any cancer cells in a lymph node count as a positive node, including isolated tumor cells.

To find these small deposits, the pathologist may cut the lymph node into thin slices and examine several levels. They may also use immunohistochemistry, a stain that highlights cancer cells. For carcinomas, this stain often targets proteins called cytokeratins, which normal lymph node cells do not make.
What is extranodal extension?
Extranodal extension means cancer cells inside a lymph node have broken through the node’s outer capsule into the surrounding tissue. Reports may also call it extracapsular extension or extranodal spread. It is reported as present or absent, and some reports add how far the cancer has spread beyond the capsule.
How much extranodal extension matters depends on the cancer. In head and neck squamous cell carcinoma that is not related to HPV, it raises the N stage under the AJCC 8th edition. A single positive node 3 cm or smaller moves from pN1 to pN2a when extranodal extension is present. In many other cancers, extranodal extension does not change the stage but is still recorded as a higher-risk feature.
Several positive lymph nodes stuck together into one mass are described as matted lymph nodes. Matting usually happens because cancer has grown through the capsules of neighboring nodes.

What is a tumor deposit, and is it the same as a lymph node?
In colon and rectal cancer, the pathologist may find a nodule of cancer in the fat beside the bowel with no lymph node tissue around it. This is called a tumor deposit. It is not counted as a positive lymph node, and the report lists it separately.
Tumor deposits still affect the stage. When all lymph nodes are negative, but tumor deposits are present, the N stage is pN1c. When some lymph nodes are already positive, the deposits are recorded but do not change the lymph node count.
Why does the number of lymph nodes examined matter?
The number of lymph nodes examined tells your doctor how confident they can be in a negative result. Finding no cancer in 2 nodes is less reassuring than finding no cancer in 20. For some cancers, guidelines set a minimum number of lymph nodes to examine.
Colorectal cancer is the best-known example. The AJCC and the UICC recommend examining at least 12 lymph nodes to stage colon cancer accurately. Some studies have questioned whether 12 is the right number, but it remains the common benchmark. Our colorectal cancer report guide walks through this part of the checklist.
A lower count does not always mean something was missed. People naturally have different numbers of lymph nodes, and nodes can shrink after chemotherapy or radiation. When the count is low, the pathologist may go back to the specimen and search the fat again. A sentinel node biopsy is designed to remove only a few nodes, so a small count is expected there.
How do the lymph node findings become the N stage?
The lymph node findings are summarized in the N part of the TNM staging system as the nodal stage. A small “p” in front means the stage is based on lymph nodes the pathologist examined. Our dictionary entry on the nodal stage and our article What Is TNM Staging? explain how N fits into the overall stage.
- pN0. No cancer was found in any regional lymph node examined.
- pN1, pN2, and pN3. Cancer was found in regional lymph nodes. Higher numbers usually mean more nodes or larger deposits, but the exact meaning differs for each cancer.
- pNX. The lymph nodes could not be assessed, usually because none were removed.
- (sn). The stage is based only on a sentinel node biopsy, as in pN0(sn).
- (i+) and mi. These suffixes mark isolated tumor cells and micrometastasis, as described above.
You may also see a “c” instead of a “p,” as in cN0. This is the clinical N stage, based on imaging or physical examination rather than the microscope. A report that says “cT1c N0” for a breast biopsy is giving a clinical stage, because no lymph nodes were removed. When lymph nodes are later removed, the pathologic N stage replaces it.
What do lymph node results mean after chemotherapy or radiation?
When treatment is given before surgery, the lymph node stage is written with a “y” in front, as in ypN0 or ypN1. The “y” tells your doctor the nodes were examined after treatment. This matters because treatment can kill cancer cells that were once in the node.
After treatment, a lymph node that once contained cancer may show scarring, called fibrosis, with no remaining cancer cells. Pathologists report this as a treatment effect. The scar is not counted as a positive node and is not included in the measurement. Only living cancer cells are measured.
The bar for a complete response in the lymph nodes is strict. In breast cancer, even isolated tumor cells remaining after treatment mean the result is not a complete pathologic response. Some breast reports also give a residual cancer burden score, which combines the remaining cancer in the breast and the lymph nodes.
What if the lymph node itself was the specimen?
Sometimes a single lymph node is removed or sampled because it is enlarged, and the report is about that lymph node alone. In this setting, the question is not how far a known cancer has spread. The question is why the node is enlarged in the first place.
- Reactive changes. The node is enlarged because it responds to infection or inflammation. Reports may say “reactive lymph node,” “reactive lymphoid hyperplasia,” or “sinus histiocytosis.” These are noncancerous findings.
- Granulomas. Small clusters of immune cells called granulomas can point to infections such as tuberculosis or to inflammatory conditions. Further tests are often needed to find the cause.
- Lymphoma. Lymphoma is a cancer that starts in the lymphocytes of the lymph node itself. It is a different disease from a cancer that has spread to a node from somewhere else.
- Metastatic cancer. The node contains a cancer that started elsewhere, such as metastatic carcinoma. Stains can often suggest where the cancer began when that is not yet known.
Lymphoma is diagnosed partly from how the cells are arranged inside the lymph node. For that reason, pathologists often prefer the whole node or a core needle biopsy rather than a fine needle aspiration. Lymphoma testing usually includes immunohistochemistry and often flow cytometry. Lymphoma is staged with the Lugano classification rather than TNM, and that stage is based mainly on imaging.
What happens after the lymph node results?
Lymph node findings are one of the main pieces of information your care team uses to plan the next steps. Along with other findings in the report, they help decide whether to consider treatment after surgery. The choices depend on the type of cancer, so your oncologist will explain what the lymph node result means for you.
The role of lymph node surgery has narrowed in some cancers. In early breast cancer, the American Society of Clinical Oncology (ASCO) updated its sentinel node guideline in 2025. It says some postmenopausal patients with small grade 1 or 2 hormone receptor-positive tumors may not need a sentinel node biopsy at all. It also says many patients with one or two positive sentinel nodes who receive breast radiation do not need the remaining armpit nodes removed.
Lymph node results can sometimes be updated after the first report. Extra stains or additional sections may be added later as an addendum. If your report says testing is still pending, our article on pending or additional testing explains what that means.
Questions to ask your doctor
- How many lymph nodes were examined, and how many contained cancer?
- Were my lymph nodes removed during surgery, or is my lymph node status based on imaging?
- Was this a sentinel lymph node biopsy or a full lymph node dissection?
- Was the cancer in my lymph nodes a macrometastasis, a micrometastasis, or isolated tumor cells?
- How large was the biggest deposit of cancer in my lymph nodes?
- Was extranodal extension present, and does it change my stage?
- Were tumor deposits found, and how do they affect my stage?
- Were enough lymph nodes examined for my type of cancer?
- What is my N stage, and is it clinical or pathologic?
- If I had treatment before surgery, did my lymph nodes show a response to that treatment?
- Do my lymph node results change whether treatment after surgery is recommended?
- Will I need more lymph node surgery or radiation to the lymph node area?
- If my lymph node was removed because it was enlarged, what caused the enlargement?
- Are any additional tests on my lymph nodes still pending?
Related articles on MyPathologyReport.com
- Lymph Nodes
- Sentinel Lymph Node
- Understanding Your Sentinel Lymph Node Biopsy Report
- Isolated Tumor Cells
- Extranodal Extension
- Nodal Stage (N Stage)
- What Is TNM Staging?
- Surgical Margins: What Negative, Close, and Positive Mean in Your Pathology Report
- Metastasis
- Tumor Deposit
- Reactive Lymphoid Hyperplasia
- Lymphoma
We are proud to partner with:


🔍 Search MyPathologyReport
Type what you see on your report — for example a diagnosis or test name