

Section Editor: Bibianna Purgina MD FRCPC
October 6, 2026
Grade 2 chondrosarcoma is a type of bone cancer made of cartilage, the firm, smooth tissue that covers the ends of bones in joints. In chondrosarcoma, the cancer cells produce cartilage instead of bone. Your report may also call it intermediate-grade chondrosarcoma.
Chondrosarcoma is one of the most common bone cancers in adults. It usually affects people aged 40 to 70. The most common locations are the pelvis, thigh bone, upper arm bone, shoulder blade, and ribs.
This article explains what grade 2 means and what the other findings in your pathology report mean.
What does grade 2 mean?
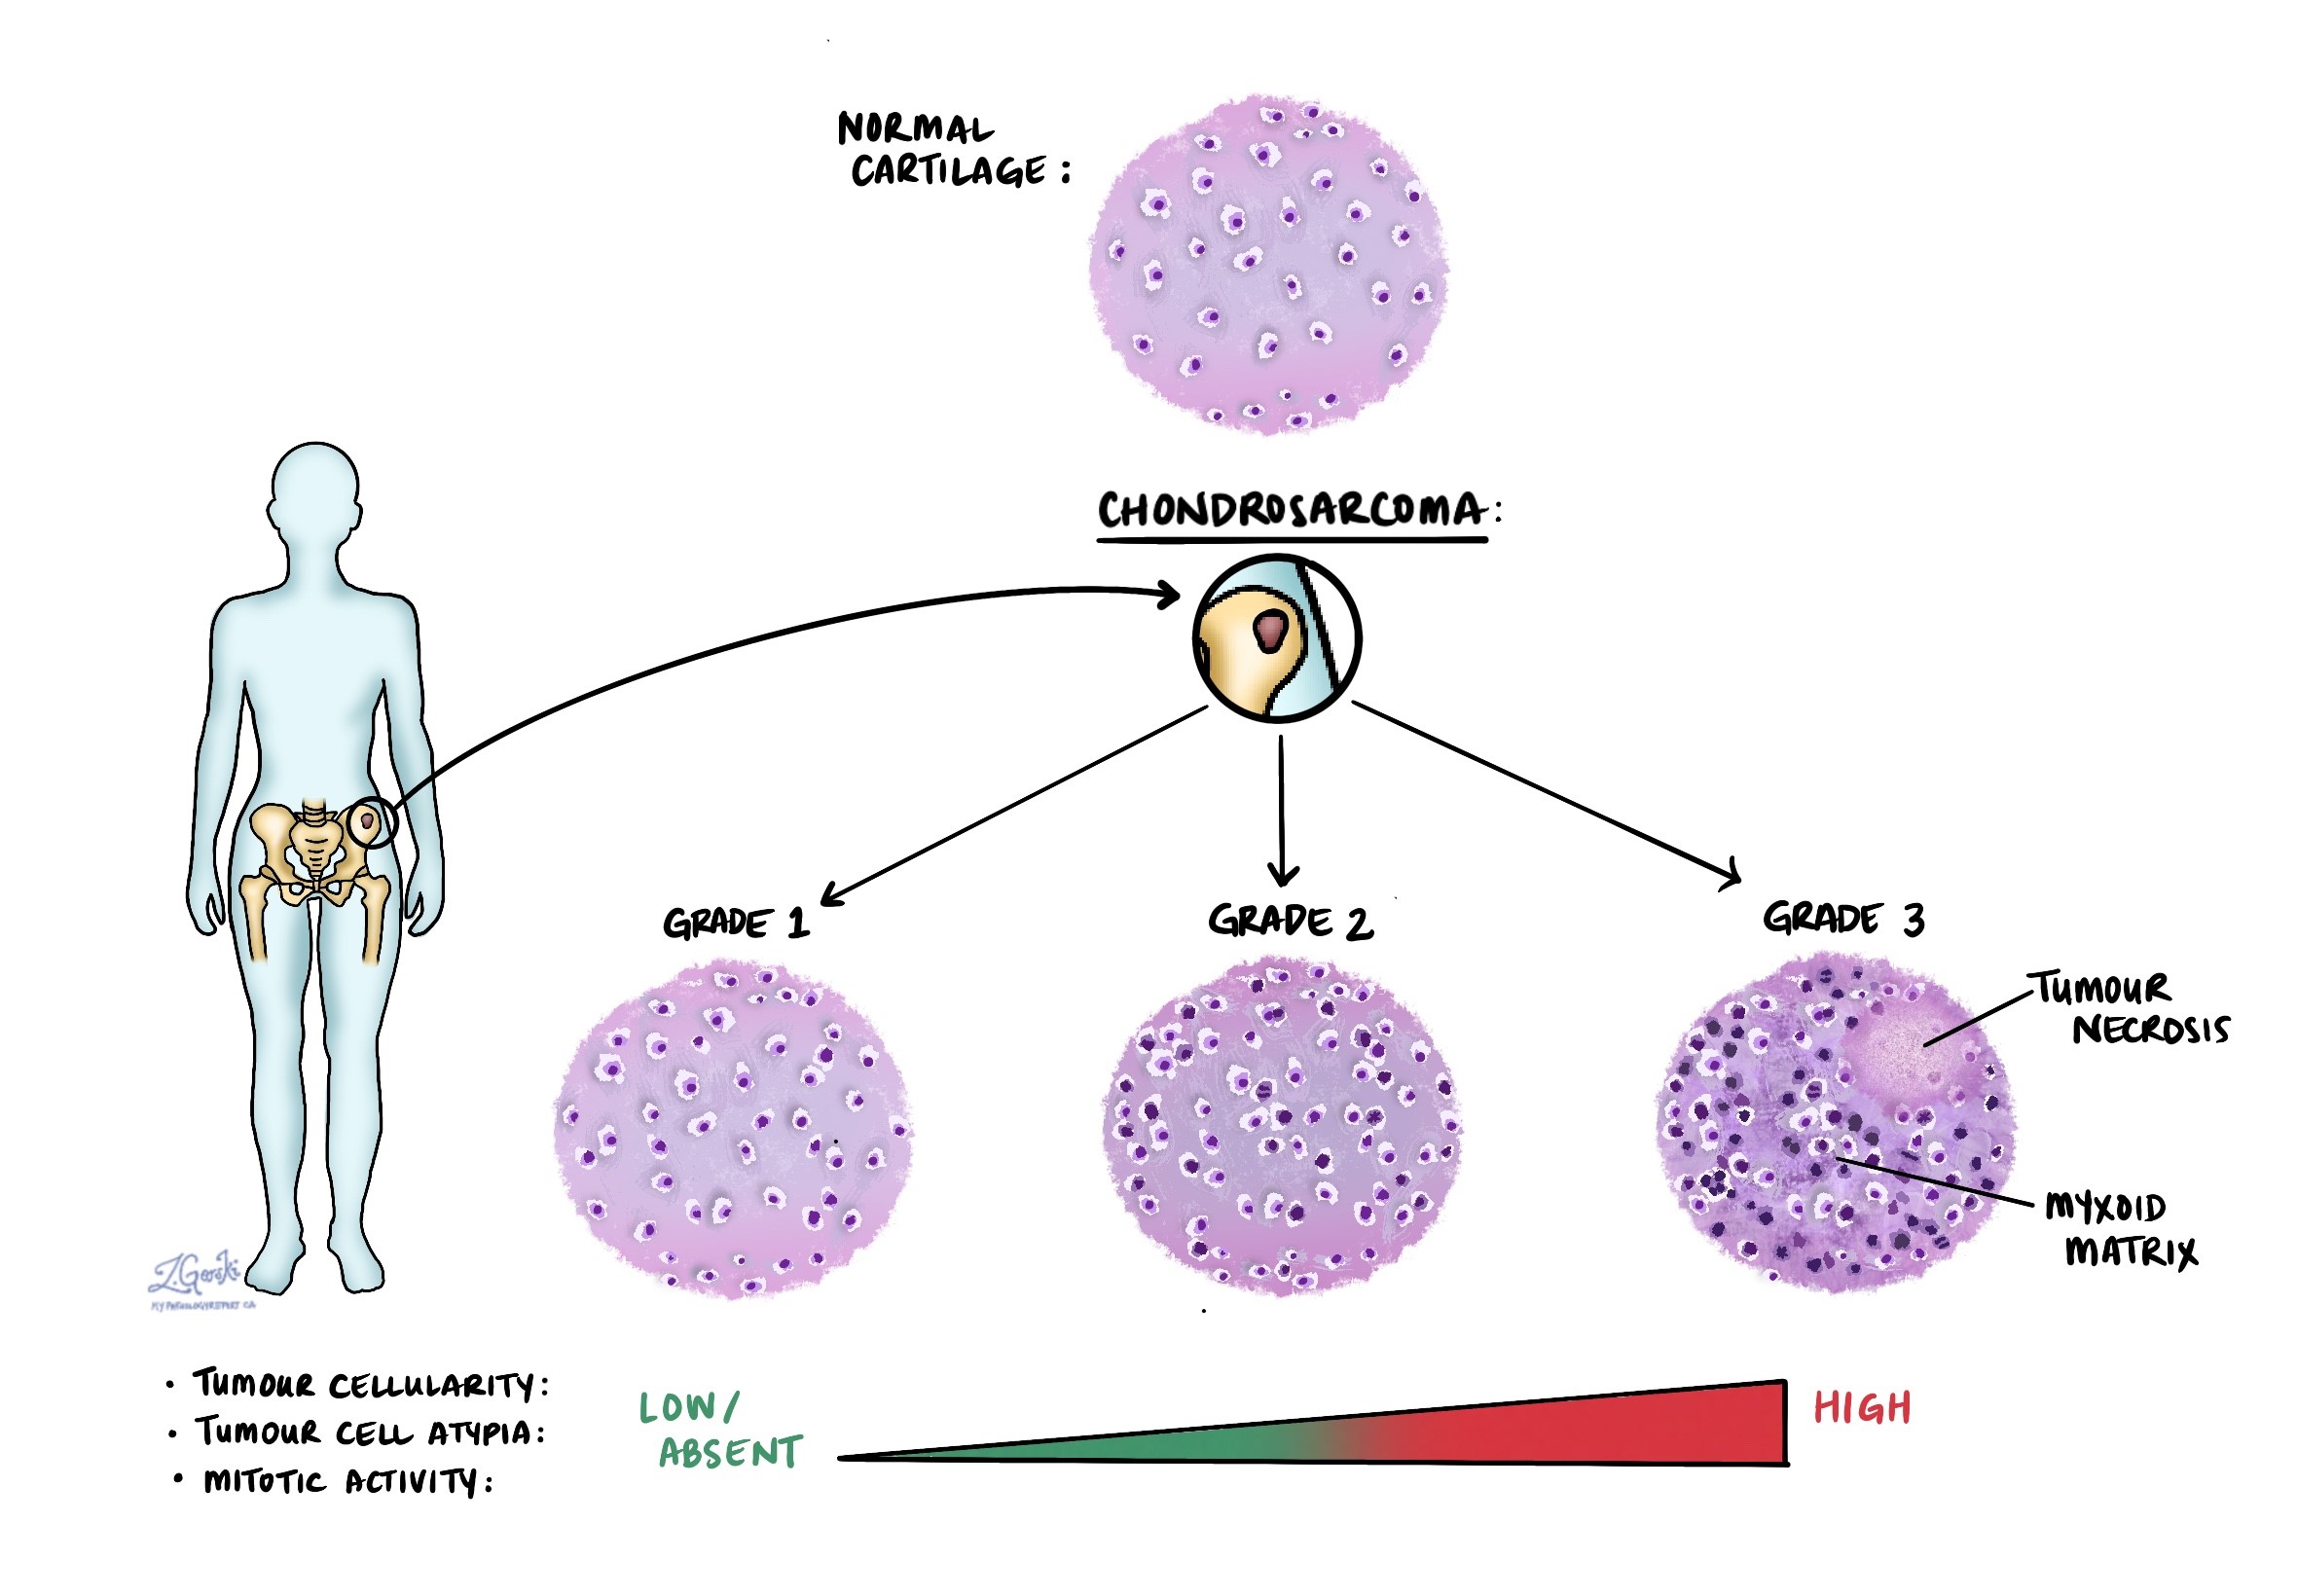
The grade describes how abnormal the cancer cells look under the microscope. It is the most important finding in a chondrosarcoma report because it is the strongest predictor of how the tumor will behave. Chondrosarcomas are given one of three grades:
- Grade 1. The cells look very close to normal cartilage cells. These tumors grow slowly and very rarely spread.
- Grade 2. The tumor contains more cells, the cells look more abnormal, and some of them are dividing. These tumors are more likely than grade 1 tumors to come back after surgery, and a minority spread to other parts of the body.
- Grade 3. The tumor is crowded with highly abnormal cells, many of which are dividing. These tumors are the most likely to spread.
Grade 2 sits in the middle. Most people with a grade 2 chondrosarcoma that is completely removed are cured, but the tumor needs more extensive surgery and longer follow-up than a grade 1 tumor.
What causes chondrosarcoma?
For most people, no cause is found. About half of chondrosarcomas that start inside the bone carry a change in a gene called IDH1 or IDH2. This change develops in the tumor cells during a person’s lifetime. It is not inherited and cannot be passed on to children.
A few conditions raise the risk of developing chondrosarcoma:
- Multiple enchondromas. People with many noncancerous cartilage tumors called enchondromas, a condition called Ollier disease, have a higher risk. The same is true of Maffucci syndrome, which combines enchondromas with blood vessel growths. Both are caused by an IDH change that occurs early in development and are not inherited.
- Multiple osteochondromas. This inherited condition causes many bony outgrowths called osteochondromas, and a small proportion of them develop into chondrosarcoma. A change in the EXT1 or EXT2 gene causes it. Each child of an affected parent has a 50% chance of inheriting it.
- Previous radiation therapy. Rarely, chondrosarcoma develops in a bone treated with radiation years earlier.
What are the symptoms of chondrosarcoma?
The most common symptom is a deep, aching pain in the affected bone. The pain often develops slowly, may be worse at night, and does not settle with rest. Some people notice a lump or swelling, and a tumor near a joint can limit movement.
New pain in a known cartilage tumor is a reason to have it checked, because it can signal that the tumor is growing.
How is the diagnosis made?
X-rays, CT, and MRI show a tumor that contains cartilage, often with small flecks of calcium. Imaging also shows whether the tumor is wearing away the bone or breaking through it.
A biopsy confirms the diagnosis. The biopsy should be done at the center that will perform the final surgery, because the track left by the needle has to be removed along with the tumor later.
Under the microscope, a grade 2 chondrosarcoma is made of cartilage cells that are more crowded than in a grade 1 tumor. The nuclei, the part of the cell that holds the genetic material, are larger and darker, a change pathologists call nuclear atypia. Some cells are dividing, which is called mitosis. Dead tumor tissue is usually absent.
Different parts of a chondrosarcoma can look different, so pathologists sometimes revise the grade after the whole tumor is removed and examined.
Molecular testing
Testing for an IDH1 or IDH2 change may be done on the tumor. Finding one supports the diagnosis and helps separate chondrosarcoma from chondroblastic osteosarcoma, a different bone cancer that also contains cartilage but is treated with chemotherapy.
IDH1 testing is also used to find people who may be eligible for clinical trials of targeted drugs, described below.
Tumor extension
Grade 2 chondrosarcoma starts inside the bone. Your report may describe whether the tumor has broken through the bone’s outer shell into surrounding muscle or other soft tissue. This is called extraosseous extension.
The report may also note whether the tumor has grown into a nearby joint or an adjacent bone. In the spine and pelvis, which are made of several connected bones, spread from one bone to another raises the stage.
Margins
A margin is the edge of tissue cut by the surgeon. For chondrosarcoma, margins are especially important because surgery is the main treatment, and tumor left behind is the main reason the cancer comes back.
- Negative margin. No cancer cells are seen at the cut edge. The report may give the distance between the tumor and the closest margin.
- Positive margin. Cancer cells reach the cut edge, and some tumor may remain. This raises the chance the cancer will come back in the same place.
Your report will usually list several margins, including the cut ends of the bone, the surrounding soft tissue, and any large blood vessels or nerves that were removed.
Stage
Bone cancers are staged using the TNM system from the American Joint Committee on Cancer (AJCC), 8th edition. The tumor stage, called pT, depends on which bone is involved:
- Arms, legs, trunk, skull, and face. The stage depends mainly on size. A tumor 8 cm or smaller is pT1, and a tumor larger than 8 cm is pT2. Separate tumor deposits within the same bone are classified as pT3.
- Spine and pelvis. These bones have their own staging rules, based on how many bone segments are involved and whether the tumor extends beyond the bone.
- Lymph nodes. Chondrosarcoma rarely spreads to lymph nodes, so surgeons usually do not remove them. When no nodes are examined, the report may say the nodal stage was not assigned.
When chondrosarcoma spreads, it usually travels through the bloodstream to the lungs, which is why a chest CT scan is part of the assessment.
What is the prognosis?
Roughly 70% to 85% of people with a grade 2 chondrosarcoma are alive five years after diagnosis. The outlook is best when the whole tumor is removed with negative margins, and the cancer has not spread.
Tumors in the pelvis and spine have a less favorable outlook than tumors in the limbs, mainly because they are harder to remove completely. A positive margin raises the chance of the tumor coming back in the same place.
Chondrosarcoma can come back many years after surgery, sometimes more than 10 years later. These figures describe groups of people and cannot predict what will happen to one person.
What happens after the diagnosis?
A team at a center that regularly treats bone sarcomas manages chondrosarcoma.
- Surgery. The main treatment is removing the tumor with a rim of normal tissue. Part of the bone may be replaced with an implant or graft. Scraping out the tumor, which is sometimes used for low-grade cartilage tumors in the limbs, is not recommended for a grade 2 tumor.
- Radiation therapy. Chondrosarcoma does not respond well to standard radiation. High-dose or proton radiation may be used when the tumor cannot be removed completely, particularly at the base of the skull.
- Chemotherapy. Standard chemotherapy works poorly for chondrosarcoma and is not routinely used.
- Targeted treatment. For tumors with an IDH1 change that cannot be removed or have spread, a drug called ivosidenib is being studied in a large clinical trial. It is not yet approved for chondrosarcoma, and your oncologist can tell you whether a trial is open to you.
- Follow-up. Regular imaging of the original site and of the chest continues for many years.
Questions to ask your doctor
- Was the grade confirmed after the whole tumor was removed?
- Was the whole tumor removed, and were all the margins negative?
- Did the tumor grow outside the bone?
- Was the tumor tested for an IDH1 or IDH2 change?
- Has the cancer spread to my lungs or elsewhere?
- Do I need any treatment after surgery?
- How often will I need follow-up imaging, and for how many years?
Related articles on MyPathologyReport.com
We are proud to partner with:


🔍 Search MyPathologyReport
Type what you see on your report — for example a diagnosis or test name