

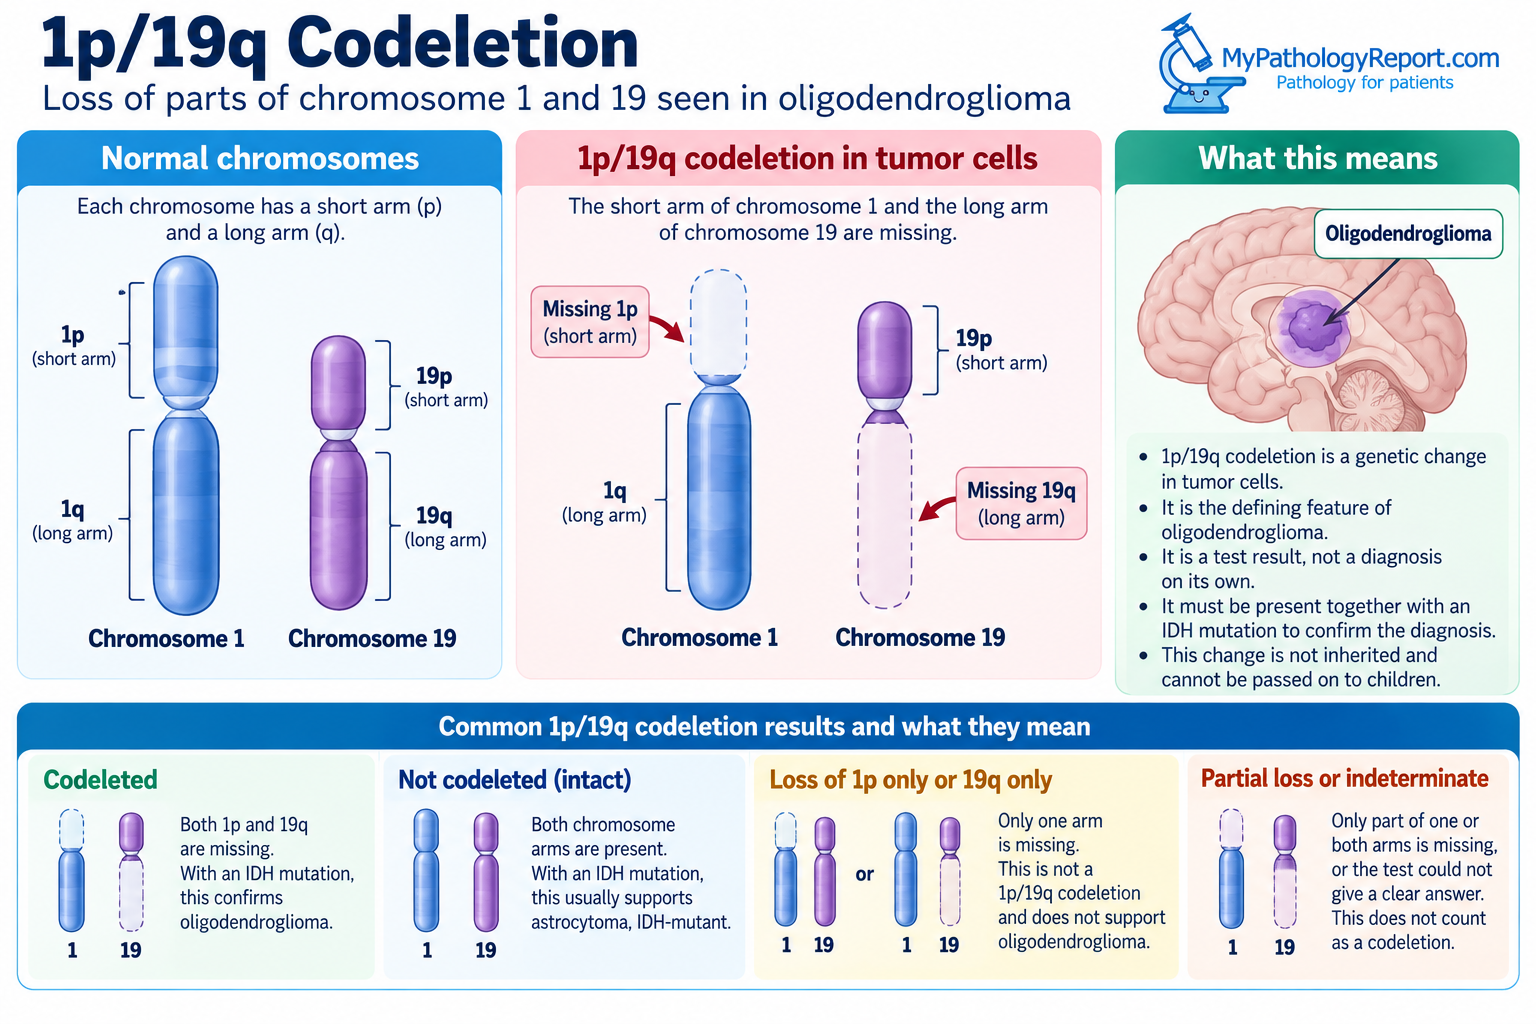
1p/19q codeletion is a genetic change in which tumor cells have lost two specific pieces of their chromosomes at the same time. One missing piece is the short arm of chromosome 1 (1p). The other is the long arm of chromosome 19 (19q). This change is the defining feature of a brain tumor called oligodendroglioma. Your report may also describe it as “1p/19q codeleted” or “loss of 1p and 19q.”
1p/19q codeletion is a test result, not a diagnosis on its own. Together with a change in the IDH1 or IDH2 gene, it confirms that a tumor is an oligodendroglioma. This article explains what 1p/19q codeletion means, how pathologists test for it, and what each possible result means for your diagnosis and care.
What does 1p/19q mean?
The name 1p/19q describes exactly which parts of the chromosomes are missing. Chromosomes are long strands of DNA inside the nucleus of every cell, and they carry the cell’s genes. Each chromosome is numbered and has two arms. The shorter arm is called “p,” and the longer arm is called “q.”
In a 1p/19q codeletion, tumor cells lose the entire short arm of chromosome 1 and the entire long arm of chromosome 19. “Codeletion” means the two pieces are lost together. This happens because the two chromosomes break and swap pieces, and the cell then loses one of the joined fragments.
The change happens only in the tumor cells. It is not inherited from a parent, it is not present in the rest of the body, and it cannot be passed on to children.
Why is 1p/19q codeletion important?
Testing for 1p/19q codeletion answers several questions about a type of brain tumor called a diffuse glioma:
- Diagnosis. Under the World Health Organization classification of central nervous system tumors (2021), an oligodendroglioma must have both an IDH mutation and a 1p/19q codeletion. The full name of the diagnosis is “oligodendroglioma, IDH-mutant and 1p/19q-codeleted.”
- Separating oligodendroglioma from astrocytoma. A tumor with an IDH mutation but no 1p/19q codeletion is usually an astrocytoma, IDH-mutant. The two tumors can look alike under the microscope, so this test is often what tells them apart.
- Outlook. Among diffuse gliomas, oligodendrogliomas with a 1p/19q codeletion tend to grow the most slowly and have the most favorable long-term outcome.
- Treatment planning. Tumors with a 1p/19q codeletion tend to respond well to chemotherapy, which helps the care team plan treatment.
Which tumors are tested for 1p/19q codeletion?
Testing for 1p/19q codeletion is done almost only on diffuse gliomas. These are brain tumors that spread into the normal brain tissue around them. The test matters most when the tumor has an IDH mutation, because the result helps distinguish oligodendroglioma from astrocytoma.
Other findings can make the test unnecessary. Oligodendrogliomas almost always keep a protein called ATRX. When immunohistochemistry shows that an IDH-mutant tumor has lost ATRX, the tumor is very likely an astrocytoma. In that situation, some laboratories do not test for 1p/19q at all.
Most other brain tumors and cancers elsewhere in the body do not use 1p/19q codeletion testing.
How do pathologists test for 1p/19q codeletion?
Pathologists test for 1p/19q codeletion using molecular tests on the tumor tissue. Common methods include:
- FISH. Fluorescence in situ hybridization (FISH) uses glowing probes that attach to small regions of 1p and 19q. Fewer signals in the tumor cells suggest those regions are missing. FISH works on routine slides, but it looks at only a small part of each arm.
- PCR-based loss of heterozygosity. This test uses polymerase chain reaction (PCR) to compare tumor DNA with DNA from normal tissue or blood. Missing regions in the tumor appear as differences between the two samples.
- Sequencing and array tests. Next-generation sequencing (NGS) and related array tests measure DNA along the whole length of each chromosome. They can show whether the entire arm is missing.
- DNA methylation profiling. This test classifies brain tumors by their pattern of chemical tags on DNA. The same test can also show whether 1p and 19q are lost.
Not every laboratory uses every method. The test chosen depends on the laboratory and the other results already available.
Why does losing the whole arm matter?
A true 1p/19q codeletion means the entire 1p and the entire 19q are missing. Some other brain tumors, especially glioblastoma, IDH-wildtype, can lose only part of 1p or 19q. A partial loss does not count as a 1p/19q codeletion and does not support a diagnosis of oligodendroglioma.
FISH looks at only a small region of each arm, so it cannot always tell a whole-arm loss from a partial one. For this reason, the 2021 World Health Organization classification requires codeletion of the entire arm. The pathologist may confirm the result with a test that looks at the whole chromosome. This is common when FISH results are unclear, or the tumor has no IDH mutation.
What do 1p/19q codeletion results mean?
Your report may describe the 1p/19q codeletion result in several ways:
- Codeleted, or 1p/19q codeletion detected. Both 1p and 19q are missing. In a tumor with an IDH mutation, this confirms a diagnosis of oligodendroglioma.
- Not codeleted, intact, or no codeletion detected. At least one of the two arms is still present. In a tumor with an IDH mutation, this usually supports a diagnosis of astrocytoma, IDH-mutant.
- Loss of 1p only, or loss of 19q only. Only one arm is missing. This is not a 1p/19q codeletion, and it does not support oligodendroglioma.
- Partial loss. Only part of one or both arms is missing. This also does not count as a codeletion.
- Indeterminate or not assessable. The test could not give a clear answer, often because the sample was too small. Another test may be done on the same tissue.
How does 1p/19q codeletion affect treatment?
A 1p/19q codeletion does not determine treatment on its own, but the care team considers it. Long-term results from two large trials, RTOG 9402 and EORTC 26951, showed that people with 1p/19q-codeleted tumors lived longer when chemotherapy was added to radiation. That chemotherapy combination is called PCV (procarbazine, lomustine, and vincristine). Some teams use another chemotherapy drug, temozolomide, instead. Trials comparing the two in codeleted tumors are ongoing.
Oligodendrogliomas also have an IDH mutation, which can be targeted directly. In August 2024, the FDA approved vorasidenib for some grade 2 astrocytomas and oligodendrogliomas. It is approved for people 12 years and older with a tumor that has a susceptible IDH1 or IDH2 mutation, after surgery. This drug targets the IDH change rather than the 1p/19q codeletion. Approval and access vary by country, and your care team can tell you what applies to you.
What might my pathology report say?
On a brain tumor report, the final diagnosis often combines the tumor type, the genetic results, and the grade in one line. For example:
- Integrated diagnosis. Oligodendroglioma, IDH-mutant and 1p/19q-codeleted, CNS WHO grade 2.
- Molecular results. IDH1 R132H mutation detected. 1p/19q codeletion detected (whole-arm).
An oligodendroglioma can be CNS WHO grade 2 or grade 3, depending mainly on how fast it is growing. The 1p/19q codeletion is present at both grades.
Questions to ask your doctor
- Does my tumor have a 1p/19q codeletion?
- Was an IDH mutation also found in my tumor?
- Does my diagnosis say oligodendroglioma or astrocytoma?
- Which test was used to check for 1p/19q codeletion?
- Did the test confirm that the whole arm of each chromosome is missing?
- Was ATRX tested, and what did it show?
- What is the grade of my tumor?
- How does the 1p/19q result affect my treatment options?
- Am I a candidate for a drug that targets the IDH mutation?
- Can this genetic change be passed on to my children?
Related articles on MyPathologyReport.com
We are proud to partner with:


🔍 Search MyPathologyReport
Type what you see on your report — for example a diagnosis or test name